Sciatica and tingling in a seated position: possible cause
21/08/2026
Sciatica and car seat: why tilt matters
21/08/2026
IN BRIEF
|
Definition: Herniated disc is the rupture of the envelope of an intervertebral disc, with protrusion of the nucleus that may compress a nerve root. It can manifest as radicular pain that radiates to the buttock and leg, and sometimes appears without marked low back pain, that is, pain without back pain. Benefits: understanding the mechanism allows prioritizing conservative treatment and maintaining activity (physiotherapy and exercises), avoiding unnecessary surgery. Functioning: in most cases, healing occurs with movement and rehabilitation, and surgery remains rare. Practical advice: prioritize gentle exercises and consult in case of warning signs to adjust treatment with a professional. |
Yes, it is possible: a herniated disc can manifest without significant back pain, resulting in pain that follows the path of the compressed nerve, often in the buttock and leg, or sometimes in the arm depending on the location.
- Radicular pain: pain radiating along the affected nerve (Sciatica for lumbar, arm pain for cervical).
- Sometimes little or no low back pain: imaging may reveal the hernia even without marked back pain.
- Possible neurological symptoms: numbness, tingling, muscle weakness in the affected limb.
- Diagnosis and management: clinical evaluation + imaging (MRI or CT scan) and conservative treatment (adapted activity, physiotherapy, analgesics); surgery is rare in cases of treatment failure or significant neurological impairment.
This article, written by a health professional, explores whether a herniated disc can cause pain without back pain. It explains the possible mechanisms, key signs, management options, and when to consult. The aim is to enlighten patients about the relationship between a herniated disc and peripheral pain, without necessarily presenting major low back pain.
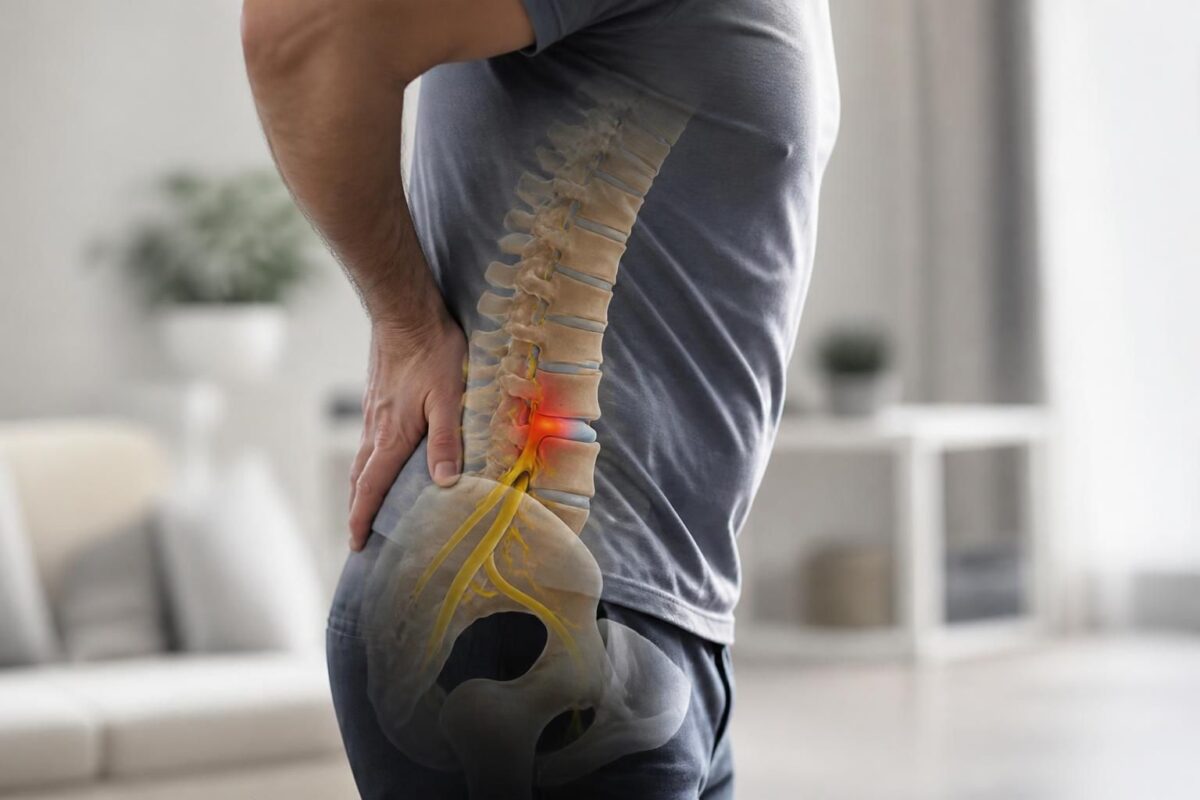
Yes, pain related to a herniated disc can appear without marked low back pain. The key lies in the fact that the pain may come from irritation or compression of a nerve root. This pain then follows the path of the affected nerve, not necessarily the lower back. In most cases, radicular pain manifests in the buttock, thigh, leg, or foot, without dominant back pain.
How a herniated disc can generate pain without low back pain
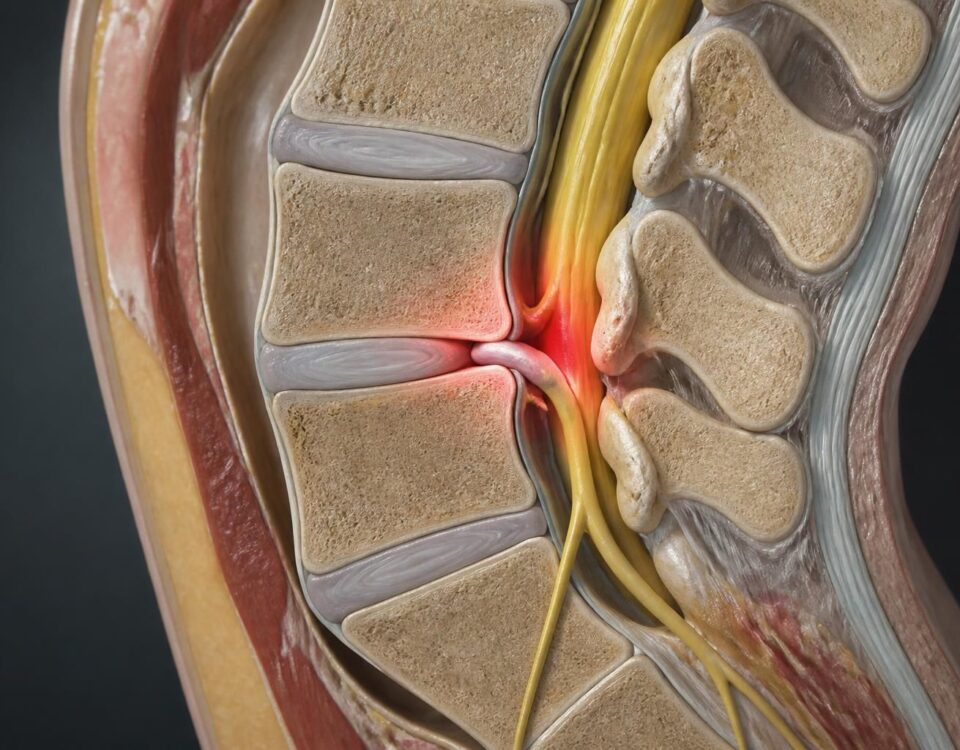
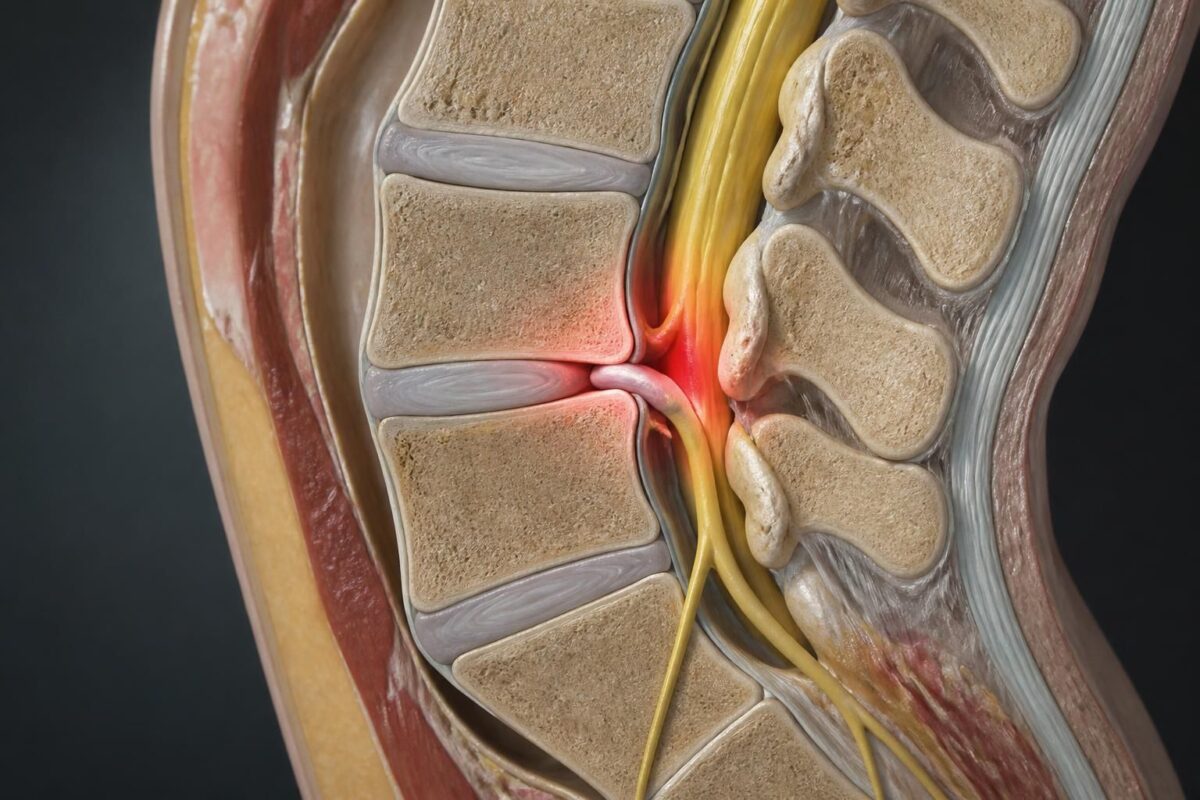
The gelatinous nucleus of an intervertebral disc can protrude through the fibrous ring and compress a nerve root. This compression triggers neuralgia or radiculopathy, producing pain, tingling, weakness, or a burning sensation in the areas innervated by the affected nerve. Pain often “follows” the path of the nerve, for example, from the buttock to the foot, even if the back is relatively painless. Approximately 85% of sciatica cases are due to a herniated disc, and lumbar hernias are the most common (nearly 95%).
Sensory and motor signs may accompany this pain: tingling, muscle weakness, or difficulty lifting the foot. In some cases, the pain is mostly felt during certain movements or positions, and may dissipate at rest, which can mask the discal origin.
Diagnosis and elements to monitor
The diagnosis is based on the clinical history and physical examination. Imaging may be necessary when symptoms persist, worsen, or present alarming signs. The use of an MRI or CT scan can help visualize the location and impact on the nerves. Warning symptoms, such as loss of urinary or bowel control, progressive weakness in both legs, or pain associated with significant neurological impairment, require urgent medical attention.
To understand the links between radicular pain and herniated disc, see the explanatory link on sciatica and herniated disc – understanding the link.
When to consider specialized evaluation
An evaluation is indicated if the pain persists beyond a few weeks, if it is accompanied by neurological impairment, or if warning signs arise. Additional resources and guides exist on reference sites, especially to understand the links between herniated disc and pain and management options.
Management options and the role of care at TAGMED clinic
Several avenues can be considered, depending on the clinical evaluation and impact on daily life. Among them:
- Non-steroidal anti-inflammatory drugs (NSAIDs) or pain relievers, used according to tolerance and under medical supervision.
- Local infiltration when pain persists despite medical treatment, after appropriate evaluation.
- Neurovertebral decompression (non-surgical techniques) when deemed appropriate by the team.
- Surgery limited to severe cases or when neurological deficits progress despite non-surgical treatments.
- Complementary approaches at the TAGMED clinic in Montreal or Terrebonne, based on indications and evaluation.
To deepen the approaches related to sciatic pain and herniated disc, consult the following resources: Herniated disc – general information, Protrusions and associated conditions, and Neurovertebral decompression. For an assessment and precise indications, you can also refer to TAGMED Clinic.
Summary Table of Approaches (Comparative)
| Therapy | Mechanism | Relative Effectiveness | Remarks |
|---|---|---|---|
| Neurovertebral decompression | Treats the nerve area involved without surgery | Varies by patient | Proposed in some cases after evaluation |
| Medication (NSAIDs, pain relievers) | Reduction of inflammation and pain | Often a temporary and transient effect | Short-term use; monitoring necessary |
| Injection (local corticosteroids) | Local reduction of inflammation around the nerve | Variable effect | Performed after evaluation and potential failure of medical treatment |
| Physical therapy | Strengthening and stability of the trunk | Variable effectiveness; often useful as a complement | To be considered in a holistic approach but not as the sole treatment |
| Surgery | Resection of the portion of the disc compressing the nerve | Often effective for leg-associated pain | Reserved for severe cases or failure of non-surgical treatments |
Prevention and Lifestyle
Prevention involves appropriate monitoring and healthy lifestyle habits. Maintaining suitable activity, avoiding heavy loads and prolonged flexed positions, and favoring positions that preserve the spine can help reduce the risk of recurrence. For specific advice, consult associated resources and discuss with your healthcare professional.
Useful Links and Resources
To delve deeper into the concepts discussed and access additional resources, consult in particular:
- Sciatica and disc herniation – explanatory link
- Sequestered disc herniation and sciatica – evaluation
- Disc herniation with foot weakness – signs to watch for
- Neurovertebral decompression – approach
- TAGMED Clinic
For information on training and professionals, relevant references are limited to NUMSS, NAO, National University of Medical Sciences, and National Academy of Osteopathy, and the associations ACMA, College of Canadian Osteopaths, and Collège des Ostéopathes Canadiens.
Medical Disclaimer: The information and advice provided on this site do not replace the opinion, diagnosis, or treatment of a healthcare professional. Please note that Dr Sylvain Desforges, osteopath, is neither a medical doctor nor a physician, and is not a specialist in a medical specialty as defined by the Collège des médecins du Québec. Manual medicine, functional medicine, and sports medicine as described on this site exclude any treatment or medical diagnosis made by a doctor or specialist physician. Always consult your doctor for any medical questions. For more details, please read our full Legal Notice.
.two-columns{ display:flex; gap:24px; }
.column{ flex:1; padding:0 8px; list-style:none; }
.column li{ margin:6px 0; }
strong{ font-weight:700; }
- Myth : low back pain is mandatory with a disc herniation.
- Myth : without low back pain, there is no disc herniation.
- Myth : a normal imaging scan (MRI) excludes disc herniation.
- Reality : radicular pain can affect the buttock/leg without low back pain.
- Reality : symptoms depend on the affected nerve and can be isolated in the leg.
- Reality : the diagnosis combines clinical examination and imaging, not solely MRI.
- Reality : conservative treatment (activity, physical therapy, pain relievers) helps in the majority of cases.

Quick summary: This article explains whether a disc herniation can cause pain without back pain, how it can present as radicular pain in the leg (sciatica), and what non-surgical recommendations to prioritize to relieve this pain while preserving back mobility.
What is a disc herniation and how can it manifest without low back pain?
A disc herniation occurs when the core of an intervertebral disc pushes through the fibrous envelope and can compress a nearby nerve root. This nerve pressure most often manifests as pain along the path of the affected nerve: in the buttock, thigh, and leg (sciatica) or, in the case of a cervical herniation, in the shoulder and arm. In some patients, low back pain may be minimal or absent, while pain in the leg predominates. The diagnosis relies on the association of pain/radicular pain and further examinations when necessary.
Signs and Warning Signals
Typical signs of radicular pain related to a disc herniation include pain that follows the path of the affected nerve, sometimes accompanied by numbness, tingling, and muscle weakness in the leg or foot. The pain can be aggravated by certain actions (coughing, sneezing, sitting for long periods, bending forward). Warning signs that require urgent consultation include urinary or anal issues, loss of sensation around the genitals or thighs (bowel movements), and weakness in both legs; these symptoms may indicate serious nerve damage and require prompt medical attention.
Non-Surgical Approaches and Practical Advice
In most cases, the management of a herniated disc relies on conservative measures that promote mobility and recovery. Adapted movement is favored over prolonged bed rest. Physical therapy and trunk strengthening exercises, combined with gentle stretches, help stabilize the spine and reduce pressure on the nerve. Maintaining good posture while standing and sitting, along with simple measures like using lumbar support or taking regular breaks to move, facilitate recovery. Acute pain can be relieved by painkillers and heat measures, alongside exercises. It is important to avoid movements that exacerbate pain and to gradually progress in daily and professional activities.
Examples of exercises and posture
Gentle and adapted exercises, performed under supervision or after instruction, may include pelvic floor and trunk strengthening, light stretching of the hamstrings and back, as well as breathing exercises to promote muscle relaxation. Adopting an upright posture at work, adjusting the seat and lumbar support, and prioritizing non-traumatic activities like walking or swimming contribute to prevention and symptom reduction. Assistive tools, such as support cushions or stretchers, temporarily relieve pain and improve comfort, but do not heal the hernia alone; they accompany rehabilitation and movement.
When to consider surgery?
Surgery is considered only in a minority of cases: when pain persists in a debilitating manner despite well-conducted treatment over several weeks, or when neurological deficits appear and worsen. The goal is to remove the portion of the disc that compresses the nerve. Even after surgery, the risk of recurrence remains and emphasis is placed on the importance of preventive measures and maintaining a strong back after surgery.
Role of osteopathy and physical therapy
An osteopathic and physical therapy approach aims to assess mobility restrictions and tensions around the spine, release tensions on the nerve root, and restore functional mobility without forcing the irritated nerve. The treatment is individualized: it focuses on improving circulation, relieving muscle tensions, and teaching daily movements that protect the spine. In addition, exercise and posture protocols tailored to the patient accelerate recovery and reduce the risk of recurrence.
| Aspect | Concise Elements |
|---|---|
| Definition | A herniated disc is caused by a tear in the intervertebral disc covering with protrusion of the nucleus that can compress a nerve. |
| Pain with or without back pain | Yes: pain along the nerve pathway, sometimes without marked low back pain; possible paresthesias or weakness. |
| Profile | More common in men, ages 35-55; factors: overexertion, poor posture; genetic predispositions. |
| Typical symptoms | Lower back pain radiating to the buttock and leg (sciatica); numbness; weakness. |
| Diagnosis | Diagnosis by clinical examination and imaging (MRI or CT scan); X-ray useful as a first step. |
| Conservative treatment | Conservative treatment: adapted activity, physical therapy, NSAIDs/painkillers; possible injection; non-surgical options often effective. |
| When surgery | Surgery considered if treatment fails or there is serious neurological impairment. |
| Prognosis | Prognosis: 90% heal without surgery; typical improvement in 3-4 months. |
| Prevention and daily life | Prevention and daily life: regular activity, correct posture, trunk strengthening; avoid prolonged rest; gradual return. |
| Accessories and aids | Accessories: lumbar cushions and stretchers relieve but do not heal; accompany movement and physical therapy. |
Testimonials on Herniated Disc and Pain without Back Pain
Testimonial 1 — Julie, 42 years old: I experienced pain that did not come from my back but from my leg. The diagnosis revealed a lumbar herniated disc with radiating pain down to my foot. No marked low back pain at first, just pain radiating and tingling in my foot. After undergoing physical therapy and targeted exercises, the pain decreased and I was able to resume my activities.
Testimonial 2 — Marc, 54 years old: My sciatica appeared without marked low back pain; an intense pain started in my buttock and went down my leg. Imaging showed a lumbar herniated disc. Thanks to physical therapy and adapted exercises, I regained mobility and comfort, and I was able to resume my daily activities without persistent pain.
Testimonial 3 — Élodie, 33 years old: A pain in my shoulder and arm appeared, without notable low back pain. The diagnosis was a cervical herniated disc causing pain radiating into my arm and shoulder. With a strengthening and posture improvement program, the pain decreased and I was able to return to my professional and sports activities.
Testimonial 4 — Thierry, 60 years old: My main pain was in my leg and buttock, with little to no back pain. The examination revealed a lumbar herniated disc. I followed an adapted rehabilitation and exercises, which allowed me to avoid surgery and return to my daily activities with well-managed pain.
Herniated Disc and Radiating Pain: Professional Profile of a Committed Osteopath
Dr. Sylvain Desforges, osteopath, practitioner in manual medicine and naturopathy, is recognized for his ability to translate the complex mechanisms of pain into concrete and personalized interventions. Founder and president of TAGMED clinics, he leads a practice focused on innovation in healthcare and enhancing his patients’ quality of life. His goal is to combine scientific rigor and a human approach to guide each individual in their healing and prevention journey.
In the context of herniated disc, his approach relies on a nuanced understanding of the link between the intervertebral disc and the nerves supplying the limbs. This pathology can manifest as intense radiating pain, described as pain following the pathway of a compressed nerve and may be accompanied by paresthesias, muscle weakness, and sometimes significant sciatica. Dr. Desforges’ main idea is that pain is not necessarily limited to localized back pain: it can radiate and interfere with daily activities, even in the absence of obvious low back pain.
His approach is based on a comprehensive and dynamic assessment of the patient. He emphasizes evidence-based care tailored to each individual, prioritizing non-surgical options whenever possible. This philosophy relies on a combination of manual techniques, postural education, and targeted exercises designed to relieve pressure on the nerve roots, restore mobility, and strengthen the muscles supporting the spine. His work is framed within a preventive perspective, aimed at reducing recurrence factors and improving spinal stability in the long term.
To enhance his therapeutic arsenal, Dr. Desforges integrates advanced technologies suited to disc herniation and associated pain. These include non-invasive approaches aimed at decompressing nerve structures, optimizing tissue vascularization, and promoting muscle recovery. These interventions are used in conjunction with a personalized therapeutic program, comprising progressive exercises, physiotherapy techniques, and lifestyle advice. The goal is to enable the patient to quickly resume useful and enjoyable activities without risking aggravation of the injury.
Dr. Desforges’ mission is clear: to provide evident and tailored care that supports functional capacity and overall well-being. He works closely with his patients to clarify symptoms, explain treatment options, and set realistic goals. His commitment is reflected in transparent communication, regular monitoring of progress, and continuous adaptation of the care plan based on clinical feedback. Through this integrated approach, he aims to transform a painful situation into an opportunity for rehabilitation and sustainable prevention.
This article explores the surprising yet documented possibility that a disc herniation can trigger radicular pain without marked local back pain. It examines how the nerve can be irritated or compressed independently of significant low back pain, how to recognize the signs, when to consult, and which treatment and prevention options are relevant based on clinical assessment. For further insight into these mechanisms, you can consult specialized resources on the link between disc herniations, protrusions, and sciatica.
Yes, it is quite possible for a disc herniation to cause pain radiating down the leg without being accompanied by marked low back pain. In these presentations, the pain may follow the path of a compressed nerve (for example, the buttock, thigh, and leg, i.e., sciatica) while the back may be relatively painless or almost asymptomatic. This possibility emphasizes the importance of a diagnosis based on the overall clinical signs and not solely on the presence of back pain. To delve deeper into this point, see the article that explores the question “Can you have a herniated disc without pain?”, as well as resources discussing cases where foraminal disc herniations directly impact sciatica.
This presentation without major low back pain can complicate diagnosis without a comprehensive evaluation. The diagnosis relies on analyzing symptoms (radicular pain, paresthesias, weakness), clinical examination, and, if necessary, imaging (MRI or CT scan) to visualize the spinal canal and the disc. To understand how these manifestations can present and be interpreted, you can consult online summaries and guides on the manifestations and causes of disc herniations and their consequences (for example, resources describing symptoms, causes, and treatments).
In clinical practice, management often favors a conservative approach tailored to pain and function: maintaining appropriate activity, rehabilitation, trunk strengthening, and postural correction, with gradual use of analgesics or anti-inflammatories when necessary. Neurovertebral decompression and other non-surgical approaches may be considered when symptoms persist, and several resources discuss these options as potential solutions in certain situations (neurovertebral decompression, when decompression is the solution). To enrich your understanding, other resources detail the mechanisms and options associated with disc pain and sciatica.
Prevention and maintenance of a functional spine remain key focuses: suitable physical activity, correct posture, and back muscle strengthening. Additional readings address these concepts and offer practical perspectives to limit risks and optimize recovery, particularly regarding cases where pain does not accompany obvious back pain.
To further explore the mechanisms and clinical implications, you can consult articles and guides on the relationships between disc herniation, foraminal, and sciatica, as well as resources dedicated to non-surgical management and decompression when necessary.
Herniated disc and chemical irritation of the nerve root
IN BRIEF In brief, Herniated disc and chemical irritation of the nerve root describe pain and dysfunction due to compression and inflammatory chemical exchanges affecting a spinal nerve root. This association explains radiating pain, abnormal sensations, and sometimes muscle weakness…
Herniated disc and mechanical compression of the nerve
IN BRIEF In brief, a herniated disc is a prolapse of the intervertebral disc that can lead to mechanical compression of the nerve root, causing pain and numbness that often radiate down the leg. This compression explains radiculopathy and sensations…
Herniated disc and nerve root inflammation
IN BRIEF In brief, lumbar disc herniation and nerve root inflammation refer to compression and irritation of a spinal root causing radiating pain, paresthesias, and sometimes muscle weakness. The mechanism combines disc protrusion and radicular inflammation, hence the importance of…

Herniated disc and peripheral pain: sign to watch out for
IN BRIEF In brief, Herniated disc is the partial protrusion of the gelatinous nucleus of an intervertebral disc through the fibrous ring, which can compress a nerve root and trigger radiating pain in the limb. The key benefits of rapid…

Herniated disc and centralizing pain: sign to interpret
IN BRIEF In brief, a herniated disc is a protrusion of the intervertebral disc that can compress a nerve root, causing centralized pain and signs such as radiating pain, numbness, and weakness. The treatment is mostly conservative: guided activity, physical…

Herniated disc and pain that travels lower after movement
IN BRIEF The Herniated Disc is a protrusion of the intervertebral disc that can compress a nerve root, leading to a pain that radiates down after a movement. The benefits include better guidance for non-surgical treatment and a gradual reduction…

Herniated disc and generic exercises: risk of poor choices
IN BRIEF In brief, the herniated disc and generic exercises can worsen the pressure on the discs and the pain if the movements are inappropriate. The advantage of personalized approaches lies in tailored exercises, controlled progression, and better recovery, while…

Herniated disc and stretches: why some movements worsen
IN BRIEF A herniated disc is the displacement of an intervertebral disc that can compress a nerve root, causing pain and limitations. In this context, certain gestures or physical practices exacerbate pressure on the spine. In short, the herniated disc…

Dr Sylvain Desforges, B.Sc., D.O., N.D., osteopath, is the founding president of TAGMED and of the ACMA association. He dedicates his practice to chronic spinal pain, low back pain and symptoms compatible with sciatica, particularly when pain radiates toward the buttock, leg, calf, foot or toes.
Through SOS Sciatique, he publishes educational content on sciatica symptoms, possible causes such as disc herniation, disc narrowing, foraminal stenosis or irritation of a lumbar nerve root, as well as non-surgical approaches that may be considered according to the evaluation. At Clinique TAGMED, care may include, depending on the case, motorized neurovertebral decompression, specific osteopathic care or precision percussion.
For an evaluation related to sciatica treatment in Montreal / Mount Royal or sciatica treatment in Terrebonne, please consult the services available at Clinique TAGMED.
Medical disclaimer
The information published on SOS Sciatique is provided for educational purposes only and does not replace a consultation, diagnosis, opinion or treatment provided by a physician or another authorized healthcare professional. The author of this article is neither a medical doctor nor a specialist in a medical specialty recognized by the Collège des médecins du Québec. The osteopathic, manual medicine or functional support approaches described on this site do not constitute medical acts and are not intended to replace medical follow-up.
Consult a physician or emergency service in cases of loss of bladder or bowel control, anesthesia in the saddle area, significant or progressive weakness in the leg or foot, fever, recent trauma, severe pain or rapid worsening of symptoms. For more details, please read our Legal Notice.