




Sciatica and disc protrusion: when a protrusion of the disc irritates a nerve root
A lumbar disc protrusion corresponds to a projection of the intervertebral disc, often more localized than a simple disc bulge. When it heads to the spinal canal or to the foramen, it can reduce the space around a nerve root and cause pain compatible with sciatica.
This pain can descend into the buttocks, back of the thigh, calf, heel, foot or certain toes depending on the level reached, the side of the protrusion and the irritated nerve root. L4-L5 and L5-S1 levels are often discussed when sciatica pain is associated with lumbar disc involvement.

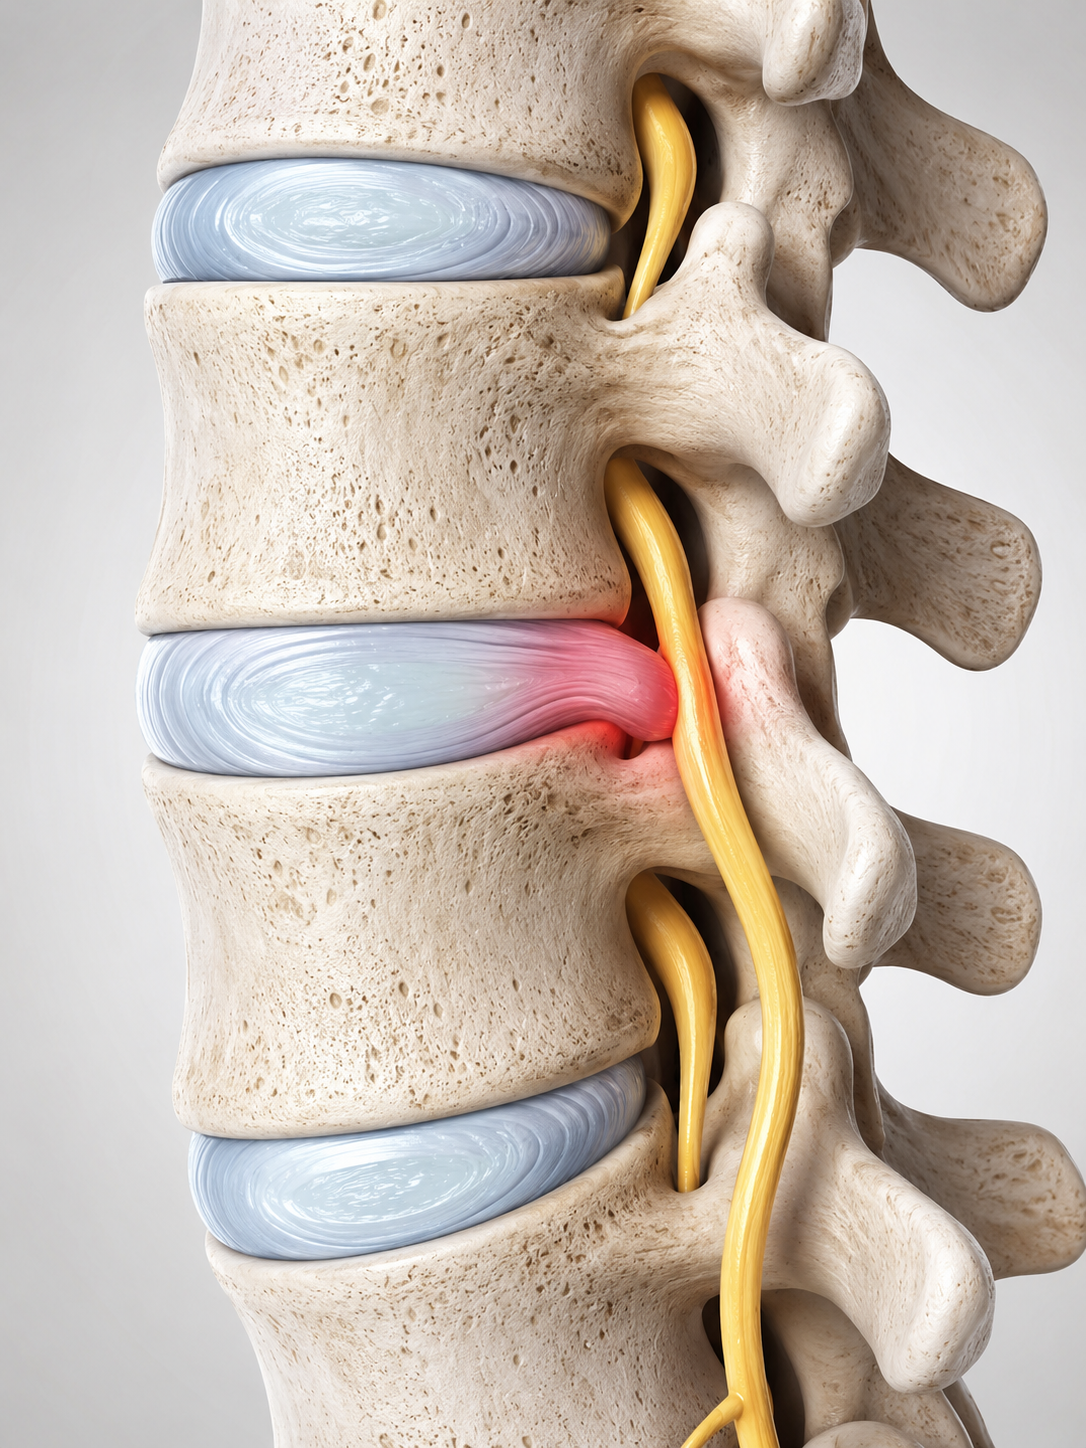
How can a disc protrusion cause sciatica?
Sciatic pain can appear when the disc protrusion comes into contact with a nerve root or reduces its passage space. Depending on the direction of the protrusion, the root can be irritated in the spinal canal, in the lateral recession or in the foramen.
The level of protrusion influences the painful territory. An L4-L5 protrusion can often be compatible with L5 irritation depending on its location. An L5-S1 protrusion may be compatible with irritation of S1 or sometimes L5 depending on the affected area.
| concerned level | Possibly irritated root | Compatible route |
|---|---|---|
| L4-L5 | L5 depending on the location of the protrusion. | Butt, side of the leg, top of the foot or big toe. |
| L5-S1 | S1 or sometimes L5 depending on the anatomical context. | butt, back of the leg, calf, heel or outer edge of the foot. |
| L3-L4 | L4 depending on the foramen or the recess concerned. | front of the thigh, knee or inner face of the leg. |
| multiple protrusions | Several possible roots depending on the level. | Mixed symptoms or less clear painful journey. |
What symptoms can accompany a disc protrusion?
A disc protrusion can be silent, cause low back pain, or contribute to downward pain if it irritates a nerve root. The table depends on the level reached, on the side, the degree of irritation and the presence of associated factors such as a disc pinch or foraminal stenosis.
lumbar pain
The pain can be felt in the lower back, especially if the disc is sensitive, cracked or overloaded.
Pain in the buttock
Deep pain in the buttocks may accompany the irritation of a lumbar nerve root.
Pain under the knee
Pain that descends under the knee, towards the calf or foot, may suggest a root component.
tingling
Tingling or electrical sensations may appear in the leg, foot or certain toes.
Numbness
A numbness in a specific territory can provide a clue to the potentially affected root.
Weakness
Difficulty lifting the foot, pushing on the tip of the foot or walking normally should be assessed quickly.
Disc protrusion, foramen and nerve root
The disc protrusion can go to the spinal canal or to the foramen. The foramen is the opening through which the nerve root comes out of the column. When the protrusion encroaches in this area, the root may lack space and become irritated.
This relationship explains why certain positions can make symptoms worse. Prolonged sitting, trunk flexion, driving or some stresses can sometimes increase stress on a sensitive disc. Conversely, some foraminal or stenosing profiles may react more to walking or standing.
- Disc protrusion: localized projection of the disc.
- foramen: passage of exit from the nerve root.
- Lateral recess: area where the root can be irritated before it exits.
- Pain under the knee: Possible sign of root irritation.
- Weakness or progressive numbness: situation to be reassessed quickly.

Protrusion, bulge, hernia or pinch: how to distinguish them?
The terms used in imaging reports are sometimes confused. They describe different disc changes, but no term alone is enough to determine the severity or exact cause of the symptoms. The key element remains clinical agreement.
| Term | What this describes | Important clinical question |
|---|---|---|
| bulge disc | more diffuse deformation of the disc beyond its usual contour. | Does the bulge correspond to the level and side of the pain? |
| Disc protrusion | more localized projection of the disc, sometimes contained but focal. | Does the protrusion affect the canal, the recession or the foramen? |
| Slipped disc | more marked movement or migration of a part of the disk. | Is there a clear conflict with a nerve root? |
| disc pinch | Decreased disc height, often linked to dehydration or degeneration. | Does the loss of height reduce the foramen or does it contribute to the symptoms? |
| Foraminal stenosis | narrowing of the nerve root exit passage. | Does the pain path correspond to the root concerned? |

Why personalized evaluation is essential
Two people may have a disc protrusion at the same level, but have very different symptoms. One may mainly have lower back pain, while the other may have pain that descends into the leg, numbness or weakness. The image alone is not enough.
At the TagMed clinic, the assessment aims to link the level of protrusion, the affected side, the path of pain, numbness, muscle strength, tolerance to sitting, walking, standing and lumbar movement. This approach makes it possible to determine whether a non-surgical and non-invasive approach can be relevant.
Clinical agreement
Compare the imaging ratio with the pain path and neurological signs.
Function and security
Check strength, sensitivity, walking, aggravating positions and evolution.
What options should be considered for sciatica related to a disc protrusion?
The choice of an approach depends on the severity of the symptoms, the level reached, the side, the duration, the presence of numbness or weakness, and the patient’s tolerance. A disc protrusion should not automatically lead to the same recommendation for all.
According to the evaluation, certain non-surgical and non-invasive approaches can be discussed, including neurovertebral decompression motorized, specific osteopathy or the precision striker. In some situations, a medical reference or other orientation may be more appropriate.
| Approach | Possible role | When to consider it with caution |
|---|---|---|
| Motorized neurovertebral decompression | Reduce some mechanical stress on discs, foramen and nerve roots. | Profile compatible with disc or mechanical irritation, with no sign of urgency. |
| osteopathy specific | Adapt the interventions to the patient’s restrictions, compensation and tolerance. | Pain associated with stiffness, limitation or mechanical overload. |
| Precision striker | Instrument assisted intervention, targeted and low amplitude. | Accurate mechanical dysfunction depending on the assessment and tolerance. |
| Medical reference | Orientation when the signs go beyond the framework of a conservative approach. | Progressive weakness, uncontrollable pain, significant loss of function or red flags. |
Sciatica, disc protrusion and Tagmed Clinic
The TagMed clinic receives patients with pain compatible with lumbar nerve irritation, especially when imaging reports mention disc protrusion, bulge, disc herniation, disc pinch or foraminal stenosis.
The typical rate is $140 per consultation or treatment. The services are not covered by the RAMQ, but osteopathy receipts may be provided and are eligible for reimbursement by several private insurance plans according to your contract.
Please note that we do not offer physiotherapy, chiropractic, injection, naturopathic or functional medicine services at the TagMed Clinic.
Tagmed Terrebonne Clinic
1150 rue Lévis, Suite 200
Terrebonne, QC, J6W 5S6
Phone: 450-704-4447
Days: Monday, Wednesday and Friday
Clinic Tagmed Montreal / Mont-Royal
1140 Avenue Beaumont
Mount Royal, QC, H3P 3E5
Phone: 1-877-672-9060
Days: Tuesday and Thursday
Frequently Asked Questions about Sciatica and Disc Protrusion
What is a disc protrusion?
A disc protrusion is a localized projection of the intervertebral disc. It can sometimes encroach on the canal, the lateral recession or the foramen, where a nerve root passes.
Does a disc protrusion always cause sciatica?
No. A disc protrusion can be visible in imaging without causing symptoms. It becomes more relevant when it corresponds to the side, level, pain path and neurological signs.
What is the difference between disc protrusion and disc bulge?
The bulging is often more diffuse, while the protrusion is generally more localized. However, terms may vary depending on the imaging reports.
What is the difference between disc protrusion and herniated disc?
Disc herniation often corresponds to more marked damage or migration of the disc material. The protrusion may remain contained, but it can still irritate a nerve root.
Can a disc protrusion irritate a nerve root?
Yes I do. If it encroaches on the canal, recession, or foramen, a protrusion can irritate a nerve root and produce descending pain in the leg.
What signs should be consulted quickly?
Progressive weakness, loss of urinary or intestinal control, stool anesthesia, rapidly aggravated pain or expanding numbness should be assessed without delay.
Can the sitting position aggravate a disc protrusion?
In some people, prolonged sitting may increase symptoms of disc origin. It is especially important to observe if the pain goes lower in the leg in a sitting position.
Is walking recommended with a disc protrusion?
It can be well tolerated in some patients, but it can also make symptoms worse in others. The reaction to walking should guide the recommendations.
Can neurovertebral decompression be considered?
It can be discussed in some profiles compatible with disc or mechanical irritation, if the evaluation does not reveal any signs of urgency or obvious contraindication.
When should a disc protrusion be evaluated again?
A reassessment is recommended if the pain persists, worsens, falls lower, limits walking, disrupts sleep or is accompanied by numbness or weakness.
Treatment pages by clinic
SOS Sciatique and TAGMED clinics are part of the same website portfolio.
Your report mentions a disc protrusion?
A personalized assessment can help link your imaging, level reached, pain path, muscle strength, and neurological signs to determine if a non-surgical approach may be relevant.
Sylvain Desforges, B.Sc., D.O., N.D., Doctor of Osteopathy

Editorial information, sources and limitations
This content is intended to inform patients about sciatica, possible causes, warning signs, and care options. It does not replace an individualized assessment.
Reference sources
References are selected according to the subject of the page: guidelines, systematic reviews, then institutional resources.
- NICE NG59 – Low back pain and sciatica in over 16s — National guideline
- HAS – Management of patients with common low back pain — French national guideline
- Cochrane – Corticosteroid injections for treatment of sciatica — Systematic review
- NCBI Bookshelf – Sciatica — Clinical institutional resource
Complementary resources from the TAGMED network
These internal resources complement the clinical information and thematic linking. They do not replace national guidelines or systematic reviews.
Editorial note on decompression
Clinical resource from the TAGMED network; it does not replace national guidelines. Some guidelines use the term “traction” and recommend caution for low back pain with or without sciatica. Any decompression option should therefore be presented as an individualized clinical approach, with limitations, indications, and contraindications clearly explained.
Limitations of this information
The information on this page is general. It does not constitute a diagnosis, prescription, or guarantee of results. Pain radiating into the leg may have several causes; assessment should consider clinical history, examination findings, symptom progression, and, when appropriate, complementary tests.
When to seek urgent medical care
Seek urgent medical care if you experience loss of bladder or bowel control, saddle anesthesia, major or progressive leg weakness, unexplained fever, pain after significant trauma, or severe pain that rapidly worsens.
