


Sciatica and bulging disc: when a curved lumbar disc irritates a nerve root
A lumbar disc bulge corresponds to a deformation of the intervertebral disc, generally more diffuse than a herniated disc. When the disc bombs backwards or sides, it can reduce the available space around a nerve root and cause pain compatible with sciatica.
This pain can descend into the buttocks, thigh, calf, foot or certain toes depending on the level reached, the side of the bulge, the irritated nerve root and the presence of other factors such as foraminal stenosis, lumbar osteoarthritis.
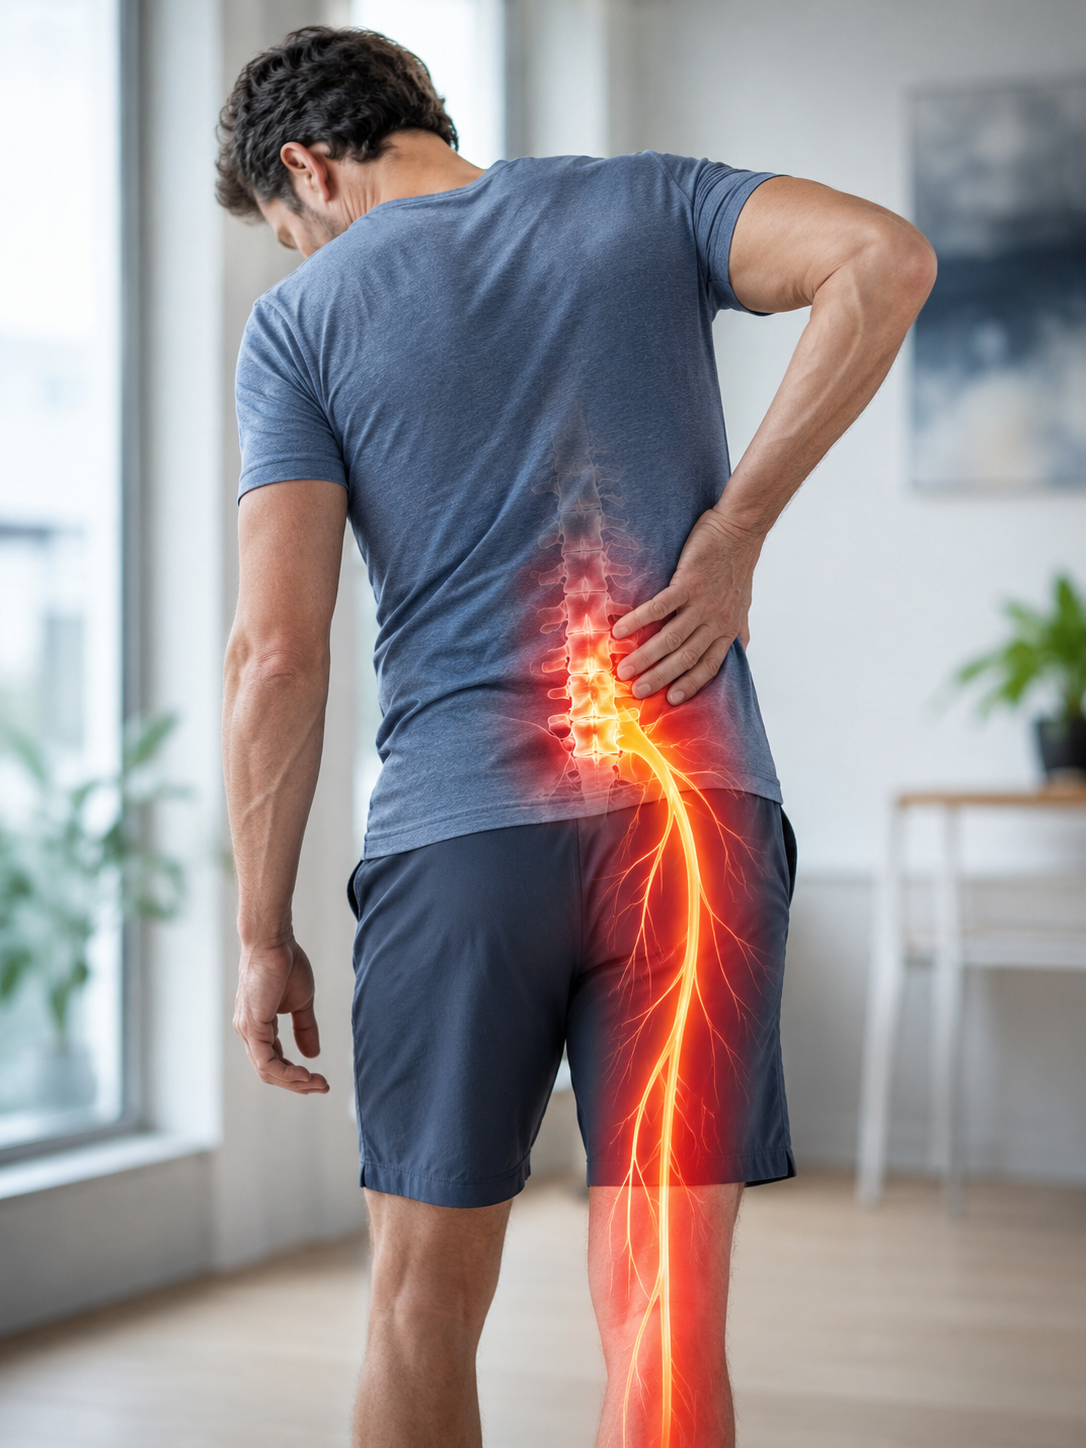
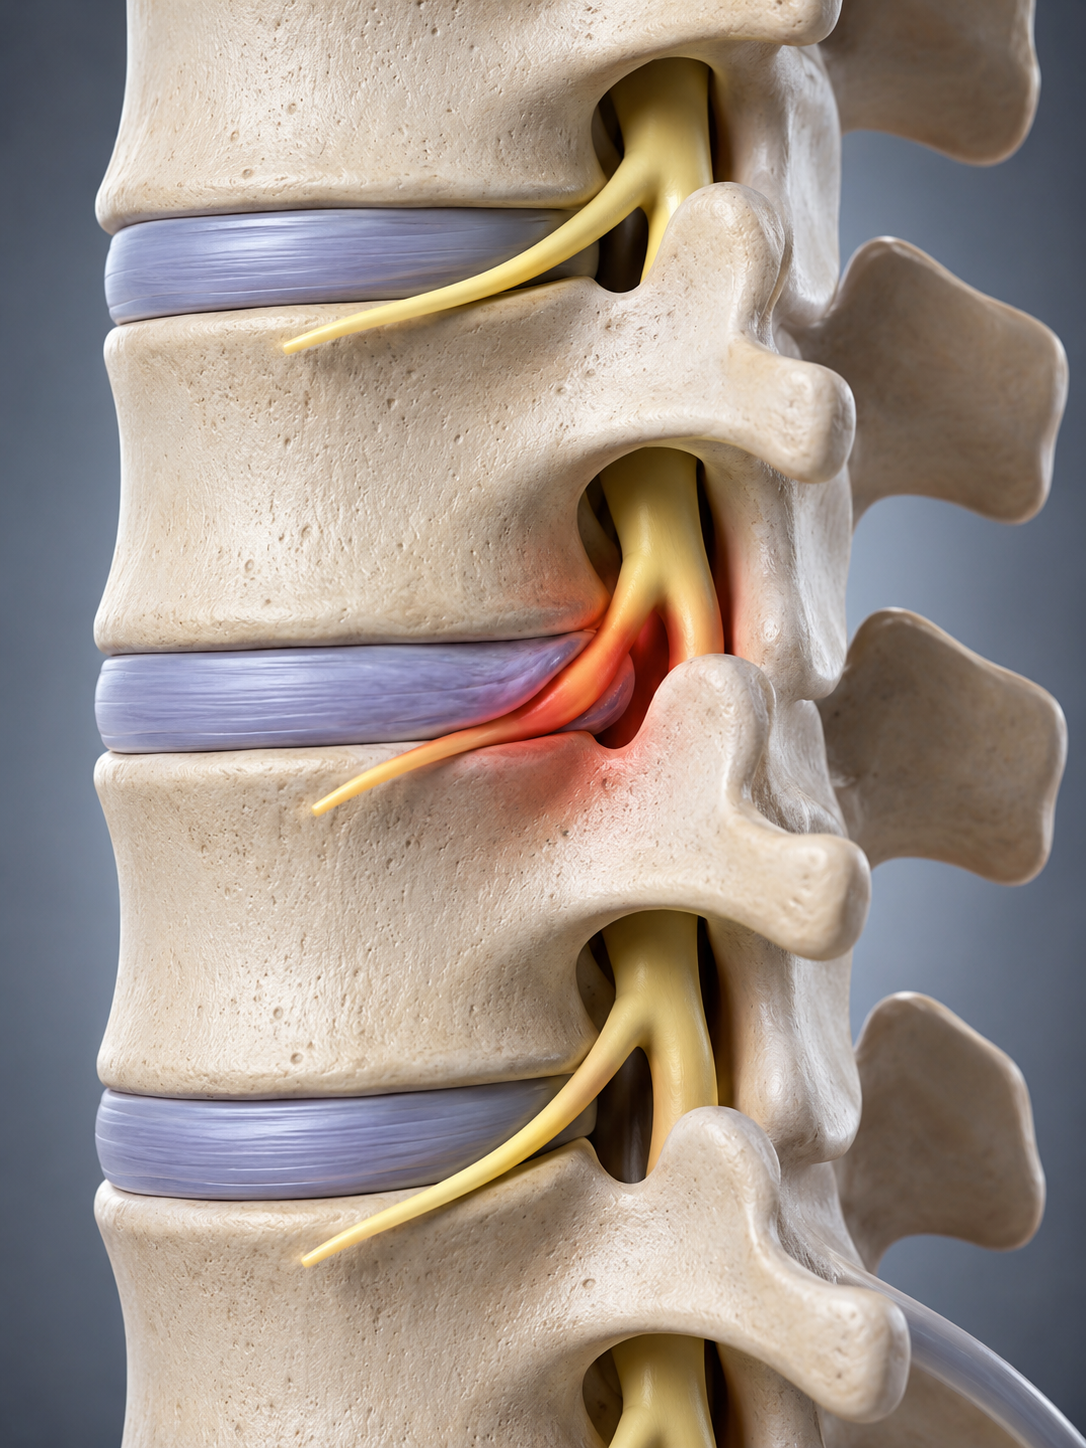
How can a disc bulge cause sciatica?
Sciatic pain may appear when the disc bulge irritates a lumbar nerve root. This irritation can be mechanical, inflammatory or linked to an already small space around the root. The bulge can sometimes be associated with protrusion, disc pinching or foraminal stenosis.
The level of the bulge influences the possible territory of the pain. A L4-L5 bulge may be compatible with L5 root irritation depending on its location. A bulge at L5-S1 may be compatible with irritation of S1 or L5 depending on the affected area.
| concerned level | Possibly irritated root | Compatible route |
|---|---|---|
| L4-L5 | L5 depending on the location of the bulge. | Butt, side of the leg, top of the foot or big toe. |
| L5-S1 | S1 or sometimes L5 depending on the anatomical context. | butt, back of the leg, calf, heel or outer edge of the foot. |
| L3-L4 | L4 depending on the location and foramen concerned. | front of the thigh, knee or inner face of the leg. |
| Multiple bulges | Several possible roots depending on the level. | mixed symptoms, less clear pain or variable irradiation. |
What symptoms can accompany a disc bulge?
A disc bulge may be silent or cause local lower back pain. When it irritates a nerve root, it can also produce falling pain in the leg, tingling, numbness or weakness depending on the root concerned.
lumbar pain
The bulging can contribute to lower back pain, especially if the disc is sensitive or overloaded.
Pain in the buttock
Deep pain in the buttock can be felt when the nerve root or lumbar structures are irritated.
Leg pain
The pain can go down to the thigh, calf, heel, foot or toes depending on the nervous territory.
tingling
Tingling can accompany root irritation, especially if the pain drops below the knee.
Numbness
Numbness in a specific territory can help identify the potentially affected root.
Weakness
Weakness of the foot, toes or calf is more worrying than isolated pain and should be assessed quickly.
bulge disc, foramen and nerve root
The disc bulge can encroach on the spinal canal or for the foramen. The foramen is the passage through which a nerve root comes out of the column. If the disc bombs in this region, the root may lack space, especially if the disc is also thinned or if osteoarthritis contributes to shrinkage.
This interaction explains why certain pains are positional. Prolonged sitting, trunk flexion, driving or some stresses can sometimes increase pressure on an already sensitive disc. In other people, walking or standing is more problematic when a foraminal or stenosing component is present.
- Disc bulge: Diffuse disc deformation.
- foramen: passage of exit from the nerve root.
- Nerve root: structure that can transmit pain to the leg.
- Pain under the knee: sign of possible root irritation.
- Weakness or progressive numbness: situation to be reassessed quickly.
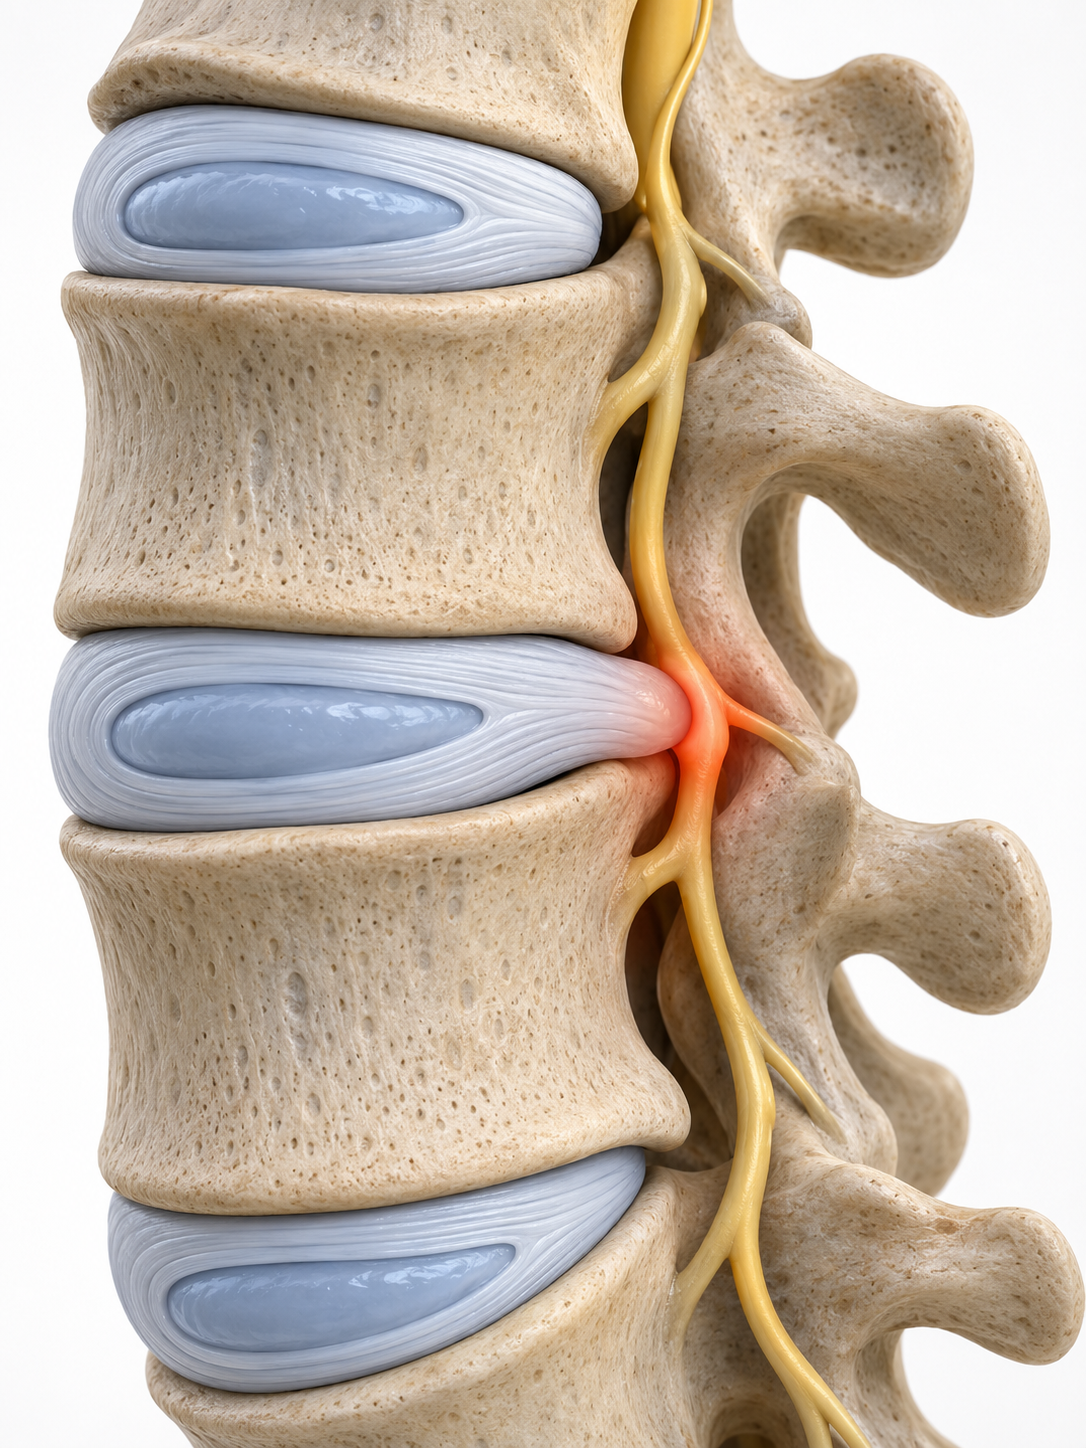
Shading, protrusion, hernia or pinching: how to distinguish them?
Terms used in imaging reports can be confusing. They describe different disc changes, but they alone do not determine the severity of the symptoms. The most important thing is to link the radiological term to the patient’s clinical picture.
| Term | What this describes | Important clinical question |
|---|---|---|
| bulge disc | diffuse deformation of the disc beyond its usual contour. | Does the bulge affect the side and level corresponding to the symptoms? |
| Disc protrusion | more localized projection of the disc, sometimes more focused than a bulge. | Does the protrusion come into contact with a nerve root? |
| Slipped disc | more marked movement or migration of a part of the disk. | Is there conflict with a root, descending pain or neurological deficiency? |
| disc pinch | Decreased disc height, often linked to dehydration or degeneration. | Does the decrease in height reduce the foramen or does it irritate a root? |
| Foraminal stenosis | narrowing of the nerve root exit passage. | Does the pain path correspond to the root concerned? |
Why personalized evaluation is essential
Two people may have a disc bulge at the same level, but have very different symptoms. One may have moderate lumbar pain, while the other may have pain that descends into the leg, numbness or weakness. The image alone is therefore not enough.
At the TagMed clinic, the evaluation aims to link the level of the bulge, the affected side, the path of pain, the location of numbness, muscle strength, tolerance to sitting, walking, standing and lumbar movements. This approach makes it possible to determine whether a non-surgical and non-invasive approach can be relevant.
Clinical agreement
Compare the imaging ratio with the pain path and neurological signs.
Function and security
Check strength, sensitivity, walking, aggravating positions and evolution.
What options should be considered for sciatica related to a disc bulge?
The choice of an approach depends on the severity of the symptoms, the level reached, the side, the duration, the presence of numbness or weakness, and the patient’s tolerance. A disc bulge should not automatically lead to the same recommendation for all.
According to the evaluation, certain non-surgical and non-invasive approaches can be discussed, including neurovertebral decompression motorized, specific osteopathy or the precision striker. In some situations, a medical reference or other orientation may be more appropriate.
| Approach | Possible role | When to consider it with caution |
|---|---|---|
| Motorized neurovertebral decompression | Reduce some mechanical stress on discs, foramen and nerve roots. | Profile compatible with disc or mechanical irritation, with no sign of urgency. |
| osteopathy specific | Adapt the interventions to the patient’s restrictions, compensation and tolerance. | Pain associated with stiffness, limitation or mechanical overload. |
| Precision striker | Instrument assisted intervention, targeted and low amplitude. | Accurate mechanical dysfunction depending on the assessment and tolerance. |
| Medical reference | Orientation when the signs go beyond the framework of a conservative approach. | Progressive weakness, uncontrollable pain, significant loss of function or red flags. |
Sciatica, bulge disc and Clinic Tagmed
The Tagmed clinic receives patients with pain compatible with lumbar nerve irritation, especially when imaging reports mention disc bulge, protrusion, disc herniation, disc pinching or foraminal stenosis.
The typical rate is $140 per consultation or treatment. The services are not covered by the RAMQ, but osteopathy receipts may be provided and are eligible for reimbursement by several private insurance plans according to your contract.
Please note that we do not offer physiotherapy, chiropractic, injection, naturopathic or functional medicine services at the TagMed Clinic.
Tagmed Terrebonne Clinic
1150 rue Lévis, Suite 200
Terrebonne, QC, J6W 5S6
Phone: 450-704-4447
Days: Monday, Wednesday and Friday
Clinic Tagmed Montreal / Mont-Royal
1140 Avenue Beaumont
Mount Royal, QC, H3P 3E5
Phone: 1-877-672-9060
Days: Tuesday and Thursday
Frequently Asked Questions about sciatica and disc bulge
What is a disc bulge?
A disc bulge is a diffuse deformation of the intervertebral disc. The disc exceeds its usual contour, which can sometimes reduce the available space around the nerve structures.
Does a disc bulge always cause sciatica?
No. A disc bulge can be visible at imaging without causing symptoms. It becomes more relevant when it corresponds to the side, level, pain path and neurological signs.
What is the difference between disc bulge and herniated disc?
The bulging is generally more diffuse. The disc herniation often corresponds to a more marked protrusion or a migration of the disc material. The actual impact depends on the irritated root and symptoms.
What is the difference between disc bulge and disc protrusion?
The protrusion is often more localized than a diffuse bulge. However, the terms may vary depending on the reports. Concordance with symptoms is more important than the word used.
Can a disc bulge irritate a nerve root?
Yes I do. If it encroaches on the canal or foramen, a bulge can irritate a nerve root and produce descending pain in the leg.
What signs should be consulted quickly?
Progressive weakness, loss of urinary or intestinal control, stool anesthesia, rapidly aggravated pain or expanding numbness should be assessed without delay.
Can the sitting position aggravate a disc bulge?
In some people, prolonged sitting may increase symptoms of disc origin. It is especially important to observe if the pain goes lower in the leg in a sitting position.
Is walking recommended with a disc bulge?
It can be well tolerated in some patients, but it can also make symptoms worse in others. The reaction to walking should guide the recommendations.
Can neurovertebral decompression be considered?
It can be discussed in some profiles compatible with disc or mechanical irritation, if the evaluation does not reveal any signs of urgency or obvious contraindication.
When should a disc bulge be evaluated again?
A reassessment is recommended if the pain persists, worsens, falls lower, limits walking, disrupts sleep or is accompanied by numbness or weakness.
Treatment pages by clinic
SOS Sciatique and TAGMED clinics are part of the same website portfolio.
Does your report mention a disc bulge?
A personalized assessment can help link your imaging, level reached, pain path, muscle strength, and neurological signs to determine if a non-surgical approach may be relevant.
Dr Sylvain Desforges, B.Sc., D.O., N.D., Osteopath

Editorial information, sources and limitations
This content is intended to inform patients about sciatica, possible causes, warning signs, and care options. It does not replace an individualized assessment.
Reference sources
References are selected according to the subject of the page: guidelines, systematic reviews, then institutional resources.
- NICE NG59 – Low back pain and sciatica in over 16s — National guideline
- HAS – Management of patients with common low back pain — French national guideline
- Cochrane – Corticosteroid injections for treatment of sciatica — Systematic review
- NCBI Bookshelf – Sciatica — Clinical institutional resource
Complementary resources from the TAGMED network
These internal resources complement the clinical information and thematic linking. They do not replace national guidelines or systematic reviews.
Editorial note on decompression
Clinical resource from the TAGMED network; it does not replace national guidelines. Some guidelines use the term “traction” and recommend caution for low back pain with or without sciatica. Any decompression option should therefore be presented as an individualized clinical approach, with limitations, indications, and contraindications clearly explained.
Limitations of this information
The information on this page is general. It does not constitute a diagnosis, prescription, or guarantee of results. Pain radiating into the leg may have several causes; assessment should consider clinical history, examination findings, symptom progression, and, when appropriate, complementary tests.
When to seek urgent medical care
Seek urgent medical care if you experience loss of bladder or bowel control, saddle anesthesia, major or progressive leg weakness, unexplained fever, pain after significant trauma, or severe pain that rapidly worsens.
