


Sciatica L5 in Montreal: pain towards the big toe
07/10/2026
Sciatica and pain after prolonged standing
07/10/2026
IN SHORT
| L5 sciatica can cause pain or numbness that radiates to the big toe, sometimes with difficulty lifting the foot. This pathway is a clue, not a diagnosis: the examination compares strength, sensitivity, and gait, as the nerve territories overlap. In Terrebonne, the evaluation helps direct an appropriate and measurable plan. New or progressive weakness requires prompt medical evaluation. |
Pain radiating from the buttock or leg to the top of the foot and the big toe may be compatible with irritation of the L5 root. A disc issue at L4-L5 may sometimes affect this root, but imaging alone cannot confirm the diagnosis: symptoms, strength, sensitivity, and gait must be assessed together.
In Terrebonne, the management plan must be tailored to the evaluation results and revised according to progress. A new or progressive weakness, a dropping foot, saddle anesthesia, or changes in urinary or bowel functions requires prompt or urgent medical evaluation.
Medical Warning: this content is educational and does not replace a consultation or diagnosis by a licensed health professional.
Pain radiating from the lower back or buttock to the top of the foot and the big toe may correspond to irritation of the L5 nerve root. This pathway provides a clue, but is insufficient to establish a diagnosis. In Terrebonne, the evaluation should also compare strength, sensitivity, reflexes, and gait before choosing treatment. The L5 root contributes to the sensitivity of part of the top of the foot and the big toe. It also aids in certain movements of the foot and toes. Irritation of this root can therefore cause pain, tingling, or numbness in these areas. Some people notice difficulty lifting the foot or the big toe. The pathway varies from person to person. Nerve territories overlap, and pain in the big toe does not confirm an L5 issue on its own. Foot pain may also have another origin. To better understand possible signs, consult this guide on L5 sciatica and the big toe or this article on pain on the top of the foot. L5 irritation can produce symptoms on the top of the foot, sometimes down to the big toe. S1 involvement may more affect the heel or outer edge of the foot. These markers remain indicative: symptoms do not always follow a clear map. The examination should compare both sides and consider all signs. Disc levels and nerve roots do not refer to the same thing. A herniation located between L4 and L5 can irritate the L5 root, while a herniation between L5 and S1 often affects S1. This relationship is not automatic. For further understanding, read this guide on L4-L5 level in Terrebonne and this resource on the differences between L4-L5 and L5-S1. Pain that follows the leg may be accompanied by burning sensations, electric shocks, tingling, or loss of sensation. Strength and gait also deserve particular attention. New difficulty in lifting the foot, a foot that catches on the ground, or progressing weakness should be quickly evaluated by a healthcare professional. Consult an emergency service in case of loss of urinary or bowel control, anesthesia around the genitals or anus, significant or rapidly progressive weakness, fever with intense pain, or recent trauma. These signs should not wait until the end of a care program. You can also check this page on nerve symptoms not to be trivialized. The evaluation begins with the timeline of symptoms, their pathway, and the activities that exacerbate or relieve them. The professional then compares strength, sensitivity, reflexes, and gait. They might check, for example, the ability to walk on heels and lift the big toe. These tests are interpreted together: no isolated sign can always identify the affected root. An MRI image is insufficient to explain a pain. Some people show a disc abnormality without symptoms. The result must correspond to the painful side, the pathway of symptoms, and the findings of the examination. To better understand this distinction, consult the article on visible disc herniation without pain. Pain near the hip or in the leg can also originate from another structure or nerve. Comparing sciatica and femoral nerve pain can help understand why the pathway alone is insufficient: sciatica or femoral nerve pain. For an overview of the nerve pathway, also check this resource on the pathway of the sciatic nerve and this guide dedicated to the L5 pathway and pain. The choice of care depends on the likely cause, the stability of strength, and the progression of symptoms. When neurological function remains stable, a non-surgical plan may be considered with defined follow-up. Options vary according to the situation and may include activity advice, manual therapy, or other approaches evaluated on a case-by-case basis. Medical or surgical intervention may be necessary in certain situations, particularly if weakness is progressing. At the TAGMED Clinic, an evaluation can help determine if treatments like specific osteopathy or motorized neurovertebral decompression are appropriate. These options may not suit everyone and do not replace a medical examination when warning signs are present. The relevance of treatment must be reassessed based on function and progress, not just a temporary variation in pain. To learn more about sciatica, you can also consult this general guide on sciatica. Before starting, it is helpful to note the activities that are challenging: walking, sitting, driving, sleeping, or working. Follow-up can then compare foot strength, walking on heels, sensitivity on the top of the foot, and the ability to resume these activities. The plan should include a re-evaluation date and signs that would lead to a change in strategy. A decrease in pain does not always prove that strength or sensitivity has returned. Conversely, a more painful day does not necessarily mean that the condition is worsening. It is essential to interpret the trend, function, and neurological status together. It is reasonable to ask what working diagnosis is being considered, what outcomes will be measured, and when the plan will be revised. No. Pain in the big toe may be consistent with L5 irritation, but it does not confirm the diagnosis. The examination must also check for strength, sensitivity, reflexes, and other possible causes. No. A herniation at this level may affect the L5 root, but imaging must correspond with the symptoms and examination results. The presence of a disc anomaly does not prove that it is causing the pain. No. Imaging is considered when its result may change management, particularly in the presence of neurological deficits, warning signs, or persistent symptoms. A healthcare professional can determine if it is relevant. New or progressive weakness, a dropped foot, numbness that spreads, or deteriorating gait justify a quick evaluation. New urinary or bowel issues, or saddle anesthesia, require urgent evaluation. Bring a timeline of symptoms, treatments already tried, a list of your medications, and available imaging reports. Also, note the affected activities and any recent changes in strength or sensitivity. Dr. Sylvain Desforges, B.Sc., D.O., N.D., osteopath, is the founding president of TAGMED and the ACMA association. His practice focuses on chronic pain of the spine, low back pain, and pain consistent with sciatica, particularly when the pain radiates to the buttock, leg, calf, foot, or toes. Through SOS Sciatique, he publishes educational content on the symptoms of sciatica, its possible causes, and non-surgical approaches that may be considered based on the assessment. At the TAGMED Clinic, care may include, depending on the case, motorized neurovertebral decompression, specific osteopathy, or precision percussion therapy. For an assessment related to sciatica treatment in Montreal / Mount Royal or sciatica treatment in Terrebonne, consult the services available at the TAGMED Clinic. The information published on SOS Sciatique is provided for educational purposes. It does not replace a consultation, diagnosis, opinion, or treatment performed by a physician or other licensed healthcare professional. The author of this article is neither a doctor nor a specialist in a medical specialty recognized by the Collège des médecins du Québec. The approaches of osteopathy, manual medicine, or functional support described on this site do not constitute medical acts and are not intended to replace medical follow-up. Consult a physician or emergency service in case of loss of urinary or bowel control, anesthesia in the saddle region, significant or progressive weakness of the leg or foot, fever, recent trauma, severe pain, or rapid deterioration. For more details, please read our Legal Notice. “Medical Disclaimer: The information and advice provided on this site do not replace the advice, diagnosis, or treatment of a healthcare professional. Please note that Dr. Sylvain Desforges, osteopath, is neither a doctor of medicine nor a physician, and is not a specialist in a medical specialty as defined by the Collège des médecins du Québec. Manual medicine, functional medicine, and sports medicine as described on this site exclude any treatment or medical diagnosis performed by a physician or medical specialist. Always consult your doctor for any medical questions. For more details, please read our complete Legal Notice.”What does pain toward the big toe mean?
L5 pain or S1 pain: pathways may overlap
Signs that require evaluation
How evaluation distinguishes possible causes
Choosing appropriate care in Terrebonne
Concrete goals for tracking progress
Frequently Asked Questions about L5 Sciatica and the Big Toe
Does pain in the big toe confirm L5 involvement?
Does an L4-L5 herniation always mean that the L5 root is involved?
Is an MRI always necessary?
What changes should be reported quickly?
What should you bring to an appointment?
About the Author
Medical Disclaimer
- Possible pathway: pain from the buttock to the top of the foot and the big toe.
- Indicators to check: numbness, difficulty lifting the foot or big toe, walking on heels.
- To nuance: nerve territories overlap; the pathway alone does not confirm L5 involvement.
- Evaluation: compare strength, sensitivity, reflexes, and gait on both sides.
- Imaging: an L4-L5 disc may affect L5, without automatic correlation with symptoms.
- Consult quickly: new or progressive weakness, dropped foot, saddle anesthesia, or urinary or bowel changes.

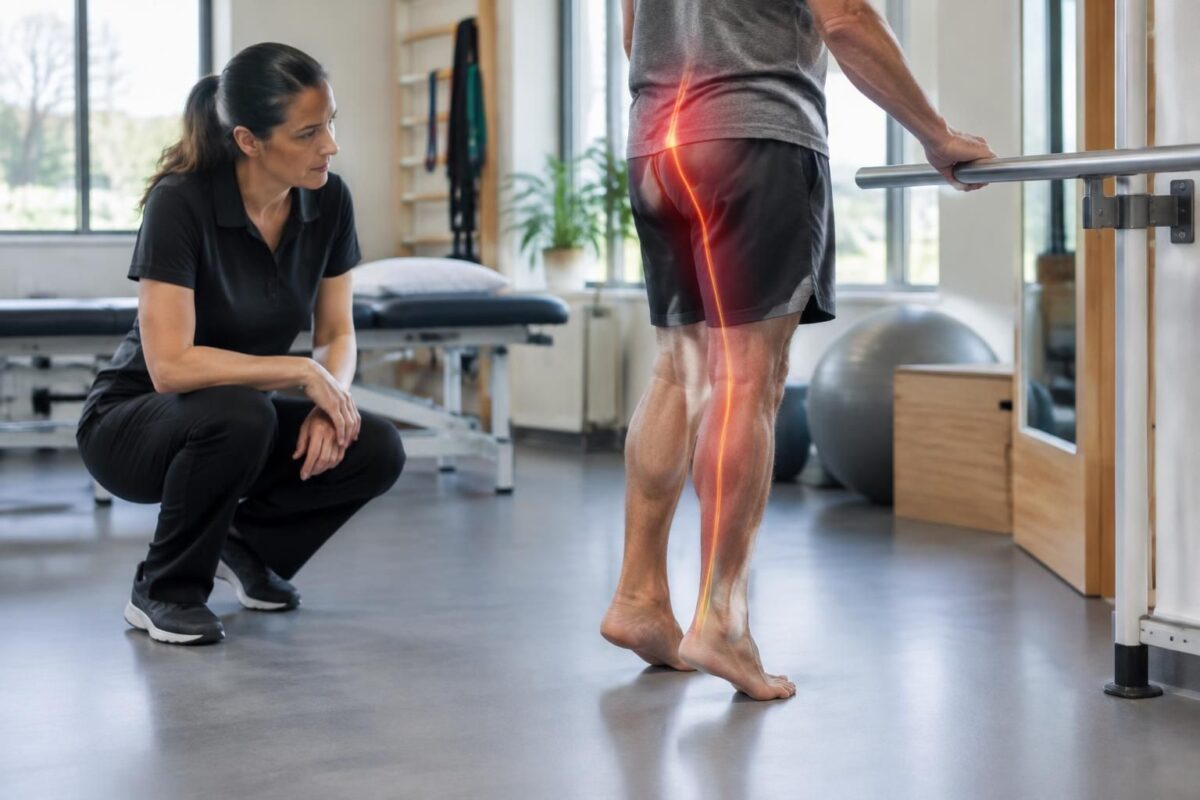
A sciatica compatible with L5 involvement can cause pain that radiates from the buttock down to the leg and the top of the foot, sometimes to the big toe. In Terrebonne and elsewhere, this pathway is an indication, not a diagnosis by itself: the evaluation must compare symptoms, strength, sensitivity, and gait before choosing care.
Why can pain reach the big toe?
The L5 nerve root is involved in sensitivity in certain areas of the top of the foot and the big toe, as well as in movements that lift the foot and big toe. Irritation of this root can therefore be accompanied by pain, tingling, or numbness in these regions.
This pathway varies from person to person. The sensory territories of L5 and S1 overlap, and pain in the big toe does not allow for certain localization of the problem’s origin. Similarly, the disc levels L4-L5 and L5-S1 do not directly indicate nerve roots: an issue at L4-L5 often affects L5, while an issue at L5-S1 often affects S1, but variations are possible.
Sciatica in Terrebonne: S1 and difficulty standing on tiptoe
IN SHORT An S1 sciatica can irritate the nerve root associated with the calf and make it difficult to rise onto the balls of the feet. This sign should be evaluated with strength, sensitivity, reflexes, and walking: the pathway of…

Sciatica in Terrebonne: L4-L5 and pain towards the top of the foot
IN BRIEF A L4-L5 sciatica can radiate to the outer side of the leg and the top of the foot, sometimes reaching the big toe. This pathway can guide the assessment, though it does not suffice to confirm the cause:…

Sciatica in Terrebonne: L5-S1 and symptoms in the calf
IN BRIEF A L5-S1 sciatica can cause pain that radiates down the calf, sometimes accompanied by tingling, numbness, or weakness. At Terrebonne, an assessment at the TAGMED Clinic helps to examine the symptom pathways, strength, and sensitivity, and then discuss…

Sciatica in Terrebonne: pain in the big toe, L5 root or another cause?
IN BRIEF Pain in the big toe accompanied by pain in the buttock or leg may be compatible with irritation of the L5 root, but other causes are possible. In Terrebonne, the evaluation notably compares strength, sensitivity, and gait to…
What signs should be evaluated?
Compare strength and gait
A healthcare professional can compare the strength of both legs, sensitivity, certain reflexes, and the way of walking. Walking on the heels, lifting the big toe, or checking if the foot drags on the ground can provide useful information. These observations must be interpreted together; no single test is sufficient to establish the cause.
Describe precisely where the pain starts, how far it goes down, and what aggravates or relieves it. Note also any changes in your sleep, your ability to walk, sit, or work. The MRI report, if there is one, can help with the assessment, but a visible anomaly on the image must correlate with the side, symptoms, and examination results.
How to choose the next steps in Terrebonne?
When neurological function remains stable, a graduated care plan can be discussed with a licensed professional, depending on the suspected cause, your preferences, and your tolerance. Activity advice, adapted exercises, or certain manual therapies may be considered after assessment. Medications, injections, and surgery fall under different indications and require discussion with the relevant professional.
Set a measurable goal from the start: walk longer, sleep better, or resume an important activity. Agree on a reevaluation time and criteria that would change the plan. A temporary improvement in pain does not alone prove that the cause is confirmed; fluctuating pain must also be contextualized with strength and function.
If symptoms change, extend, or do not progress as expected, a new assessment may be preferable to the automatic repetition of the same care. Imaging or a medical referral is considered when results may change the course of action, especially if neurological deficit appears.
When to consult quickly?
A new or progressive weakness, a dropped foot, or worsening walking requires quick medical evaluation. Consult the emergency room in case of loss of urinary or bowel control, numbness in the saddle area, significant or rapidly progressive weakness, fever, or recent trauma.
About the author
Dr. Sylvain Desforges, B.Sc., D.O., N.D., osteopath, is the founding president of TAGMED and the ACMA association. His practice focuses, among other things, on chronic spinal pain, lower back pain, and symptoms compatible with sciatica.
Through SOS Sciatique, he publishes educational content on symptoms, possible causes, and non-surgical approaches that may be considered based on the assessment. The care offered at the TAGMED Clinic may include, depending on the case, motorized neurovertebral decompression, specific osteopathy, or the precision impactor.
Medical warning
This content is provided for educational purposes and does not substitute for a consultation, diagnosis, or treatment by a physician or other licensed health professional. The author is neither a physician nor a specialist in a medical specialty recognized by the Collège des médecins du Québec. The approaches of osteopathy, manual medicine, or functional support do not constitute medical acts and do not replace medical follow-up.
| Marker | To check |
|---|---|
| Pain compatible with L5 | Buttock, side of the leg, top of the foot, or big toe. |
| Foot strength | Ability to lift the big toe and the foot. |
| Walking | Compare walking on heels on both sides. |
| Sensitivity | Identify any area of numbness and track its evolution. |
| Discal level | L4-L5 may affect L5, without automatic correlation. |
| Assessment in Terrebonne | Compare symptoms, strength, sensitivity, and function. |
| Reassessment | Set a date and measurable functional goals. |
| Urgent signs | Progressive weakness, dropped foot, or urinary or bowel disorders. |
L5 Sciatica in Terrebonne: Illustrative testimonials about pain toward the big toe
Important: the stories below are fictitious and composite examples created for educational purposes. They do not correspond to verified patient testimonials or guaranteed outcomes. Pain reaching the big toe may be compatible with irritation of the L5 root, but the symptom trajectory alone is insufficient to establish a diagnosis.
Illustrative story — pain toward the top of the foot. “My pain started in the lower back, went through the buttock, and descended on the side of the leg to the top of the foot. It was mainly the big toe that felt numb.” This type of description can guide the evaluation, but other causes can produce similar symptoms.
Illustrative story — discomfort while walking. “I felt jolts right into the big toe and felt like my foot caught more when I walked.” Difficulty in lifting the foot or the big toe deserves particular attention. A new or worsening weakness should be assessed quickly by a healthcare professional.
Illustrative story — variable symptoms. “Some days, the pain went down to the foot; other days, it mainly stayed in the buttock and thigh.” Symptoms can fluctuate. To track their evolution, it is useful to note their trajectory, activities that aggravate or relieve them, as well as changes in strength, sensitivity, and ability to walk.
How L5 can be assessed: the examination notably compares the strength to lift the foot and big toe, the sensitivity of both legs, reflexes, and walking, including on heels. The territories of L5 and S1 overlap; no isolated symptom allows for certain localization of an affected root. A discal level observed on imaging does not automatically correspond to a specific root: it must be correlated with symptoms and clinical examination.
In Terrebonne, as elsewhere, the choice of care depends on the assessment, neurological stability, functional objectives, and evolution. When strength remains stable, a graduated non-surgical plan may be considered with follow-up and reassessment criteria. If symptoms extend, walking deteriorates, or no measurable functional progress appears, the plan should be reconsidered rather than automatically repeated.
Consult quickly in case of new or progressive weakness, dropped foot, or numbness spreading. New urinary or bowel disorders, loss of sensitivity in the saddle area, or significant weakness require urgent medical evaluation.
About the author
Dr. Sylvain Desforges, B.Sc., D.O., N.D., osteopath, is the founding president of TAGMED and the ACMA association. His practice focuses, among other things, on chronic spinal pain, lower back pain, and symptoms compatible with sciatica.
Medical warning
This information is provided for educational purposes and does not replace a consultation, diagnosis, or treatment by a doctor or another licensed healthcare professional. The author is neither a doctor nor a specialist in a medical specialty recognized by the Collège des médecins du Québec. Osteopathy, manual medicine, or functional support approaches do not constitute medical acts and do not replace medical follow-up.
L5 Sciatica in Terrebonne: pain that descends to the big toe
L5 sciatica can cause pain that starts in the lower back or buttock and descends down the leg, sometimes all the way to the top of the foot and the big toe. It may be accompanied by burning sensations, shocks, tingling, or an area with reduced sensitivity. However, the pathway varies from person to person: the territories of the nerve roots overlap and do not allow for a certain identification of the cause or the level involved.
In Terrebonne, as elsewhere, the diagnosis should not rely solely on an MRI image or the location of the pain. The terms L4-L5 and L5-S1 refer to spaces between vertebrae, while L5 and S1 refer to nerve roots. A disc injury at L4-L5 often affects the L5 root, but this correspondence is not systematic. The examination must correlate the symptoms, the affected side, strength, sensitivity, reflexes, and relevant imaging results.
During an assessment, the professional may compare the ability to lift the foot and the big toe, walk on the heels, and maintain a normal gait. They also check the sensitivity of different areas of the leg and foot, reflexes, and response to back movements. The hip, peripheral nerves, and other structures can sometimes produce symptoms resembling sciatica. An MRI is therefore not automatically necessary: it is primarily considered when its result may alter management, especially if symptoms persist or if a neurological deficit is observed.
The choice of care depends on the probable cause, the evolution, and the neurological function. When this remains stable, a graduated management approach can be discussed with a healthcare professional. This may include adapted activity, progressive exercises, or manual therapy depending on the assessment and tolerance. Medications, injections, and surgery are subject to specific indications and should be discussed with qualified professionals. A serious plan specifies the goals and the timing of reassessment, rather than promising a fixed number of sessions.
To track progress, it is helpful to note pain levels, numbness, walking distance, sleep, and activities that have become difficult. Foot strength and the ability to walk on heels can also be compared over time. A temporary decrease in pain does not alone confirm nerve recovery; conversely, an isolated painful episode does not necessarily mean that the condition is worsening. It’s the overall trend, in conjunction with function and neurological examination, that helps decide whether to maintain or revise the plan.
A new or progressive weakness, a foot drop, increasing difficulty in walking, spreading numbness, or recent changes in urinary or bowel control require prompt medical evaluation. A loss of sensitivity in the saddle area, significant weakness, fever, or rapidly worsening pain warrants urgent consultation. One should not delay this evaluation to complete an already started care program.
About the author: Dr. Sylvain Desforges, B.Sc., D.O., N.D., is an osteopath and founding president of TAGMED and the ACMA association. His practice particularly focuses on chronic spinal pain and symptoms compatible with sciatica. The approaches mentioned should be tailored to each situation and do not replace medical evaluation when necessary.
Medical disclaimer: this content is for educational purposes and does not replace a consultation, diagnosis, or treatment by a licensed healthcare professional. The author is neither a doctor nor a specialist in a recognized medical specialty. In the presence of warning signs, consult a doctor or an emergency service.
In Terrebonne, pain that descends from the buttock or leg to the top of the foot or big toe may be compatible with irritation of the L5 nerve root. However, this pathway alone is not enough to establish a diagnosis: the examination must also compare strength, sensitivity, reflexes, and walking, and relate these observations to symptoms and, if relevant, imaging.
L5 Sciatica in Terrebonne: interpreting pain towards the big toe
An injury to the L5 root may be accompanied by pain, tingling, or numbness on the top of the foot and near the big toe. Some people also experience difficulty lifting the foot or the big toe, or walking on their heels. These signs are clues to check, and not an infallible diagnostic map: sensory and motor territories vary and overlap. To learn more about tingling in this area, consult our article on the possible L5 root in case of tingling in the big toe.
It is also important to distinguish the level of the disc from the affected nerve root. L4-L5 and L5-S1 refer to disc spaces; L5 and S1 refer to nerve roots. Therefore, a disc anomaly on an MRI does not, by itself, prove that it explains the symptoms. A protrusion may affect a root, but its relevance depends on its concordance with the painful side, the pathway of symptoms, and the examination results. To better understand this link, see the guide on disc protrusion and irritation of a nerve root.
Comparison with S1 can also help guide the assessment. Pain towards the heel or the outer edge of the foot may evoke another territory, without confirming it alone. The L5 and S1 pathways overlap: the examination can compare, among other things, the elevation of the big toe, walking on heels and on toes, sensitivity of both legs as well as certain reflexes. To delve deeper into this distinction, consult the guide on pain towards the heel or foot associated with L5-S1 levels in Terrebonne.
Foot pain can sometimes occur even if the lower back hurts little or not at all. This presentation does not automatically conclude to sciatica: the hip, a peripheral nerve, or other causes can produce similar symptoms. The guide dedicated to foot pain without lumbar pain in Terrebonne presents elements to discuss during an evaluation. General resources on causes, symptoms, and possible care are also available from Chirurgie du rachis Paris, Body House Kiné, and Chirurgie Rachidienne.
In Terrebonne as elsewhere, the care plan should be tailored to the working diagnosis, neurological evolution, the person’s preferences, and their functional goals. When strength is stable, non-surgical care may be considered based on the evaluation and tolerance, with a follow-up reassessment planned. Monitoring should measure concrete changes: ability to walk, to lift the foot, to sleep, to work, or to gradually resume an activity. A temporary improvement in pain does not necessarily confirm the suspected cause; the evolution of function and neurological signs also matters.
A new or progressive weakness, a foot drop, or deteriorating gait justify a prompt medical evaluation. New urinary or bowel disturbances, loss of sensation in the saddle area, or significant weakness necessitate urgent assessment. In the presence of these signs, do not delay seeking consultation to complete a care program. Additional information on toe numbness can be found in the guide on loss of sensation in the toes.
To prepare for a consultation, note the onset and evolution of symptoms, the activities or positions that modify them, the treatments already tried, and the changes observed in gait or strength. Bring available imaging reports and ask what signs support the working diagnosis, what results will be monitored, and when the plan will be reassessed. The resource from Clinique TAGMED on L5 sciatica also presents information related to this clinical picture and local evaluation.
For general information on sciatica and its various causes, you can also consult the page of Chirurgie du rachis Paris. These resources do not replace an individual evaluation and do not allow for online diagnosis.
About the author
Dr. Sylvain Desforges, B.Sc., D.O., N.D., osteopath, is the founding president of TAGMED and the ACMA association. He dedicates his practice to chronic spinal pain, low back pain, and pain compatible with sciatica, particularly when the pain radiates to the buttock, leg, calf, foot, or toes.
Through SOS Sciatique, he publishes educational content on the symptoms of sciatica and its possible causes, as well as on non-surgical approaches that may be considered based on the evaluation. At Clinique TAGMED, care may include, as appropriate, motorized neurovertebral decompression, specific osteopathy, or precision impact therapy.
For an evaluation related to treatment of sciatica in Montreal / Mont-Royal or treatment of sciatica in Terrebonne, consult the available services at Clinique TAGMED.
Medical Disclaimer
The information published on SOS Sciatique is provided for educational purposes and does not replace a consultation, diagnosis, opinion, or treatment performed by a physician or another licensed healthcare professional. The author of this article is neither a doctor nor a specialist in a medical specialty recognized by the Collège des médecins du Québec. The approaches of osteopathy, manual medicine, or functional support described on this site do not constitute medical acts and are not intended to replace medical follow-up.
Consult a physician or emergency service in case of loss of bowel or bladder control, numbness in the saddle area, significant or progressive weakness of the leg or foot, fever, recent trauma, severe pain, or rapid worsening. For more details, please read our Legal notice.

Sciatica in Terrebonne: why the affected root changes the pain path
IN BRIEF Sciatica is a pain related to the irritation of a lumbar nerve root, the path of which varies depending on the affected root. Damage to L5 can radiate to the top of the foot, while damage to S1…

Sciatica in Terrebonne: L4-L5 disc, L5-S1 disc, and leg pain
IN BRIEF Sciatica is pain that travels down the leg when a nerve root is irritated. An injury to the L4-L5 disc often affects the L5 root; an L5-S1 injury affects the S1 root. The path of the pain and…

Sciatica in Terrebonne: understanding lumbar levels on an MRI
IN BRIEF Sciatica may be related to irritation of a lumbar nerve root. A lumbar MRI shows the disks and nerves at different levels, such as L4-L5 or L5-S1, to help identify an abnormality and compare it with symptoms. In…

Sciatica L4-L5 in Terrebonne: possible pain, numbness, and weakness
IN BRIEF L4-L5 sciatica refers to pain related to irritation of a nerve root in the lower back. It can radiate to the buttock and leg, with numbness or weakness. Identifying these symptoms helps guide evaluation and care. In Terrebonne,…

Dr Sylvain Desforges, B.Sc., D.O., N.D., osteopath, is the founding president of TAGMED and of the ACMA association. He dedicates his practice to chronic spinal pain, low back pain and symptoms compatible with sciatica, particularly when pain radiates toward the buttock, leg, calf, foot or toes.
Through SOS Sciatique, he publishes educational content on sciatica symptoms, possible causes such as disc herniation, disc narrowing, foraminal stenosis or irritation of a lumbar nerve root, as well as non-surgical approaches that may be considered according to the evaluation. At Clinique TAGMED, care may include, depending on the case, motorized neurovertebral decompression, specific osteopathic care or precision percussion.
For an evaluation related to sciatica treatment in Montreal / Mount Royal or sciatica treatment in Terrebonne, please consult the services available at Clinique TAGMED.
Medical disclaimer
The information published on SOS Sciatique is provided for educational purposes only and does not replace a consultation, diagnosis, opinion or treatment provided by a physician or another authorized healthcare professional. The author of this article is neither a medical doctor nor a specialist in a medical specialty recognized by the Collège des médecins du Québec. The osteopathic, manual medicine or functional support approaches described on this site do not constitute medical acts and are not intended to replace medical follow-up.
Consult a physician or emergency service in cases of loss of bladder or bowel control, anesthesia in the saddle area, significant or progressive weakness in the leg or foot, fever, recent trauma, severe pain or rapid worsening of symptoms. For more details, please read our Legal Notice.


