Sciatica and loss of balance: symptom to assess
12/09/2026
Sciatica and calf pain while walking
12/09/2026
IN BRIEF
| In brief, the disc pinch and herniated disc refer to two distinct mechanisms affecting the intervertebral disc. The disc pinch corresponds to a loss of height of the disc, leading to contact between the vertebral end plates and an arthritic process related to degeneration and dehydration of the disc. The herniated disc occurs when the nucleus migrates through the annulus and can compress a nerve root. In many cases, the hernia may have preceded the pinch; even if the hernia partially regresses, the disc may remain pinched, signifying frequent wear in the spinal columns. Understanding these mechanisms helps guide non-surgical approaches and preventive measures tailored to the patient, and may be relevant in a local context for those suffering from low back pain and sciatica. In Montreal, this topic is particularly useful for patients seeking tailored solutions. |
Herniated disc and disc pinch represent two different mechanisms that explain spine-related pain, without being identical in their origin or clinical manifestation.
- Herniated disc: displacement or extrusion of the nucleus pulposus through the fibrous ring, potentially compressing a nerve root and causing radiating pain depending on the affected level.
- Disc pinch: decreased height of the disc due to degeneration and dehydration, leading to the closeness of the vertebral end plates and promoting facet osteoarthritis; a degenerative mechanism that may exist without hernia but can coexist with it.
This article compares two distinct mechanisms that explain low back and radicular pain: disc pinch and herniated disc. The pinch corresponds to a loss of height of the disc due to degeneration and dehydration. The herniated disc is the protrusion of the nucleus pulposus through the fibrous ring, which can put pressure on a nerve root. These mechanisms can coexist and require precise assessment to guide treatment.
Conceptual Differences
The disc pinch reflects a progressive wear of the spine. When the disc loses its height, the vertebral end plates come closer together. Bony thickening called bone spurs may appear and promote an arthritic mechanism. This phenomenon is generally related to disc degeneration and is common: it is estimated that nearly 80% of spines show signs of wear with age. The disc pinch may be present without significant radicular symptoms, but it can also coexist with other situations.
The herniated disc occurs when the nucleus pulposus migrates through the fibrous ring. This migration can irritate or compress a nerve root and cause pain that follows the path of the affected nerve, sometimes associated with motor weakness. The term “protrusion” is sometimes used interchangeably, which can lead to confusion and requires clarification during assessment.
Clinical Signs and Diagnostic Implications
The disc pinch often manifests as degenerative low back pain and may be accompanied by a feeling of stiffness. The herniated disc can present as pain that radiates to the buttock, leg, or foot, with or without muscle weakness, depending on the location and nerve innervation involved. In cases of foot weakness or other marked neurological signs, medical monitoring is necessary, and further investigations may be indicated.
To better understand the distinctions between herniated disc and disc pinch, consult specialized resources that explain the differences between these terms and their clinical implications on sosSciatique and related resources.
Management Options and Limitations of Physiotherapy
Management of both mechanisms relies on a thorough assessment and may include case-specific non-surgical approaches. At the TAGMED Clinic, care may involve motorized neurovertebral decompression, specific osteopathy, or the use of a precision percussor, depending on the individual assessment. These approaches aim to reduce mechanical strain and promote a return to activity, without prescribing inappropriate exercises or stretches within the scope of the discussed injuries. To learn more about the mechanisms and options, see the following resources: Neurovertebral decompression and prevention of future hernias, and Herniated and protruded disc: often confused terms. Other complementary articles address the distinctions between pinch and hernia and the inflammatory or irritating mechanisms around the nerve root: Difference between disc pinch and herniated disc, chemical irritation of the nerve root, and neurovertebral decompression and recurrent hernias.
For additional information on clinical distinctions and mechanisms, you can also consult resources dedicated to low back pain and sciatica and specialized resources on protrusion and disc hernia.
In therapeutic approaches, it is essential to prioritize options available at the TAGMED Clinic in Montreal or Terrebonne and to avoid proposals that have not demonstrated sufficient efficacy, especially in physiotherapy, when necessary or when recommendations do not apply to the current case.
To deepen the mechanisms and distinctions, also check the articles on annular tear and pain and on herniated disc with foot weakness.
To place these mechanisms in the overall context, training and professional practice resources refer to recognized institutions such as NUMSS, NAO, National University of Medical Sciences, and National Academy of Osteopathy, and recommend coordinated approaches with professional associations like ACMA and the College of Canadian Osteopaths.
• Neurovertebral decompression and other alternative approaches: consult dedicated resources and associated publications to understand the indications and limitations of each option.
“Medical disclaimer: The information and advice provided on this site do not replace the opinion, diagnosis, or treatment of a health professional. Please note that Dr. Sylvain Desforges, osteopath, is neither a doctor of medicine nor a physician, and is not a specialist in a medical specialty as defined by the College of Physicians of Quebec. Manual therapy, functional medicine, and sports medicine as described on this site exclude any treatment or medical diagnosis made by a physician or medical specialist. Always consult your doctor for any medical questions. For more details, please read our full Legal Notice.”
Herniated disc
- Origin: degeneration and dehydration of the disc, the nucleus migrates through the annulus.
- Effect: compression of a nerve root, radicular pain depending on the level.
- Context: often associated with disc wear and may indicate a history of previous hernia.
Disc pinching
- Origin: loss of disc height due to dehydration and wear; approximation of vertebral endplates.
- Consequences: arthritic mechanism and risk of foraminal stenosis.
- Signs: low back pain, stiffness and possible radicular irritation without major extrusion.

This guide clarifies two distinct mechanisms behind low back and radicular pain: the herniated disc and the disc pinching. They share similar symptoms but are based on different processes, which influences management approaches and potential outcomes. Here is how to distinguish them and what benchmarks to adopt for effective management.
Herniated disc: nucleus ejection mechanism
The herniated disc corresponds to a protrusion of the pulpy nucleus through the fibrous annulus, potentially irritating a nerve root and causing pain that follows the path of the affected nerve, sometimes associated with isolated low back pain or neurological symptoms.
Pathophysiology
The disc is structured by a swollen and hydrated nucleus surrounded by a stronger annulus. Over time or in the face of repeated stress, the annulus may weaken and yield, allowing the nucleus to push and touch neighboring nerve structures. This dynamics can be preceded or followed by episodes of disc wear; sometimes, a hernia retracts partially, but the disc may remain partially prominent and “pinch” a root.
Clinical signs and diagnosis
Low back pain associated with pain radiating into the buttock, leg, or foot, sometimes with paresthesias or targeted weakness. The diagnosis relies on clinical examination and imaging (MRI or CT) to locate the protrusion and assess its effect on the nerve root.
Non-surgical approaches
For many situations, conservative management is effective: maintaining an appropriate activity, pain management, trunk rehabilitation program, and strengthening exercises, as well as ergonomic advice. Targeted manual therapies and decompression techniques may be considered after thorough assessment, always in a logic of symptom reduction and prevention of recurrence.
Disc pinching: degeneration and progressive wear
The disc pinching describes the reduction of disc height due to dehydration and degeneration, a progressive process that alters the relations of vertebral elements and may promote arthritis of adjacent joint structures.
Pathophysiology
With age and/or after episodes of overload, the disc loses water volume and flexibility, which reduces its height. This shrinkage may be accompanied by degenerative signs in foraminal and facet joints. Pinching does not necessarily mean acute pain but prepares a conducive ground for low back pain and mechanical stiffness.
Clinical signs and diagnosis
Diffuse or focal low back pain, stiffness and discomfort during movements; sometimes referred pain in a buttock or thigh. Imaging reveals a reduction in disc height and peripheral degenerative signs, without necessarily showing an active hernia.
Management approaches
The strategy is based on maintaining an appropriate and progressive activity, trunk stabilization and strengthening exercises, and pain relief measures. Gentle manual therapies and rehabilitation programs can reduce symptoms and improve mobility, while delaying degenerative progression. The goal is to optimize function and prevent recurrences, without necessitating surgery unless there is a specific indication.
Disc herniation and disc narrowing: two distinct mechanisms
| Mechanism | Brief description |
|---|---|
| Disc herniation | Protrusion or extrusion of the nucleus pulposus through the fibrous ring, which may compress a nerve root and cause radiating pain. |
| Disc narrowing | Reduction of disc height due to degeneration and dehydration; contact between vertebral endplates and arthritic reaction. |
Testimonials on Disc Herniation and Disc Narrowing: Two Different Mechanisms
I was struck by a disc herniation that compresses a nerve root and triggers pain that starts in the back and radiates to the buttock, then down the leg. After a comprehensive evaluation and non-invasive treatments offered by the clinic, the pain decreased, and I regained some of my mobility, allowing me to resume my daily activities with greater peace of mind.
For me, disc narrowing is a wear and tear that leads to a loss of disc height and increased contact between the vertebral endplates. This degenerative mechanism can promote arthritic changes and persistent lower back pain. Thanks to a personalized program focused on mobility, strengthening, and stability, I noticed a gradual improvement in pain and flexibility, and a better posture in my daily life.
In the study of spinal pain, two key mechanisms emerge to describe disc injuries: disc herniation and disc narrowing. Although they involve the same anatomical compartment, they correspond to distinct evolutionary processes that influence both symptoms and management prospects.
Disc herniation occurs when the nucleus pulposus, normally contained in the center of the disc, pushes through a weakness in the fibrous ring. This extrusion can directly irritate a nerve root or compress the spinal canal, causing pain in the corresponding territory and often sciatica when the location is lumbar. The mechanism is initially localized and acute, but its evolution is very variable: in some patients, the herniated material may spontaneously resolve, while the ring may remain fragile, predisposing to recurrent episodes. The disc, however, remains marked by structural changes that may persist and influence the mobility and stability of the spine.
Disc narrowing, on the other hand, refers to a lasting reduction in disc height, a direct consequence of a degenerative process and progressive dehydration of the nucleus. When the disc loses its height, the vertebral endplates come closer together, and osteophytic edges may form, giving rise to bone spurs and a set of arthritic signs at the posterior joints. This narrowing may lead to foraminal constriction and diffuse irritation of nerve structures, not necessarily due to herniated material, but from subtle instability and compression over movements. In some individuals, narrowing may coexist with previous hernias where the content has retracted, leaving a thinner and stiffer disc, marked by wear typical of an aging spine.
From an evolutionary standpoint, disc narrowing is considered the result of a degenerative process that can begin very early, with progressive wear of the disc and changes in adjacent structures. In practice, it is observed that even in younger patients, episodes of previous disc herniation can precede or accompany this degenerative phenomenon, making narrowing a frequent step in the “muffling” of the disc rather than its simple isolated collapse. A majority of spines today show signs of wear, underscoring the largely degenerative nature of this mechanism and the issues of prevention and early management.
Understanding these two mechanisms allows for a different orientation of diagnosis and treatment plans. In modern practice, the choice of interventions is based on clinical and radiological evaluation, aiming to distinguish radicular pain related to herniation from mechanical or foraminal pain associated with narrowing. Non-surgical approaches—targeted rehabilitation, pain management, and mobility optimization—remain fundamental, but some technologies integrated into a multidisciplinary approach can support recovery. Tailored options exist to help restore function and limit symptoms, considering the specifics of each mechanism and the individual patient’s progression. A personalized approach may include complementary therapies aimed at stabilizing the spine and improving quality of life while modulating risk factors and movement habits that fuel these two mechanisms.
This article presents two distinct mechanisms that explain pain related to the intervertebral disc: disc herniation and disc narrowing. The disc herniation corresponds to an extrusion or protrusion of the nucleus pulposus that can compress a nerve root and cause pain that follows the path of the nerve (radiculopathy). The disc narrowing, for its part, describes a loss of disc height due to degeneration and dehydration, which brings the vertebral endplates closer and may promote arthritic changes at the posterior joints. These mechanisms can evolve separately or together, and understanding them helps guide the choice of examinations and treatments. A previous trigger of disc herniation may lead to a gradual narrowing of the disc over time, a common wear phenomenon in the spine.
These two mechanisms present different manifestations and implications for diagnosis and management. Disc narrowing is essentially a degenerative disease of the disc, associated with loss of height and secondary arthritic changes; disc herniation is a structural issue where the nucleus migrates and may compress a nerve root, causing pain that can extend toward the limbs. The evolution can vary with age and the rate of disc dehydration; in some cases, marked narrowing may exist without active herniation, and vice versa. To better understand these mechanisms and their practical implications, consult the recommended resources: Disc Herniation and Peripheral Pain, Disc Herniation – MSD Manual, Degenerative Discopathy with Disc Narrowing, Paramedian Disc Herniation and Sciatica.

Disc herniation and tingling in the toes
IN BRIEF A disc herniation is a disc that bulges beyond its contour; tingling in the toes can sometimes be related to irritation of a lumbar nerve, without MRI sufficiently confirming the cause. An examination connects the image, symptoms, and…

Disc herniation and numbness in the foot
IN BRIEF A disc protrusion is a bulging of a spinal disc; it does not always cause symptoms. If it irritates or compresses a lumbar nerve root, it may lead to tingling or numbness in the foot. An evaluation helps…
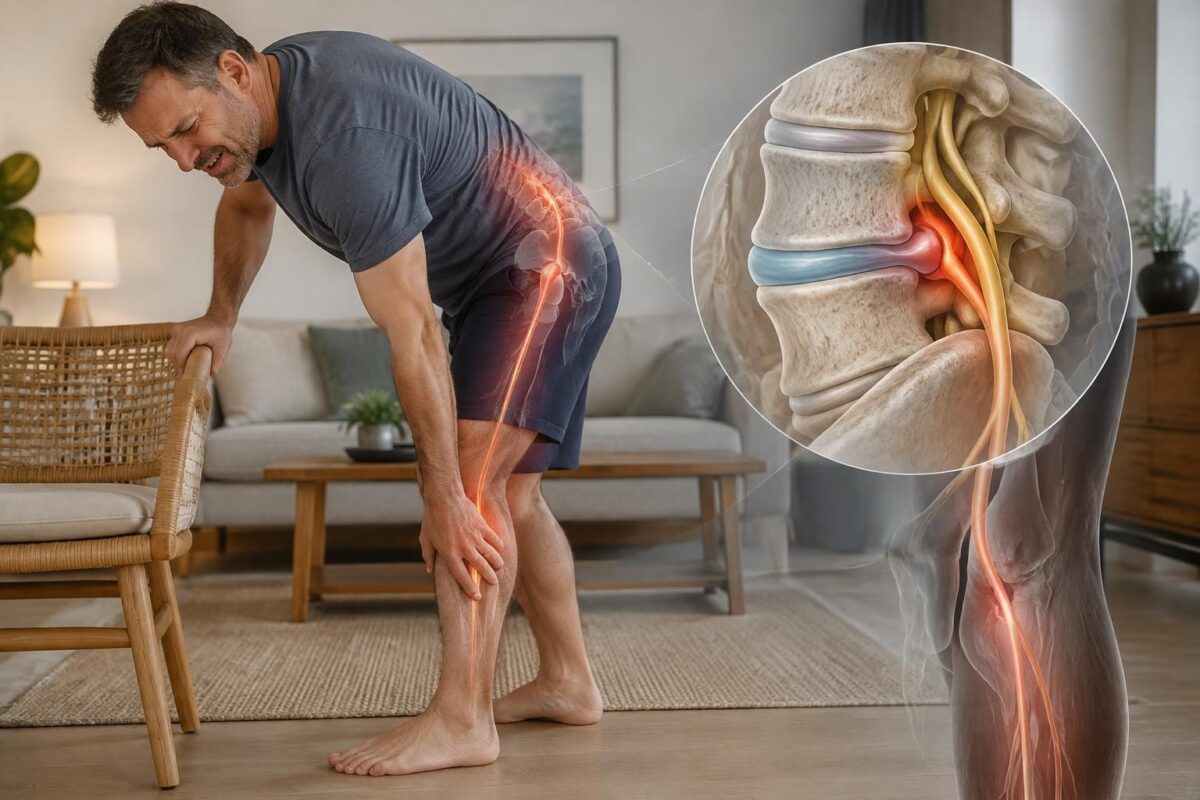
IN BRIEF A disc protrusion is a bulging of a disc that can irritate a nerve root and cause pain radiating down into the buttock and the calf, sometimes with tingling. However, it does not always cause symptoms. Evaluation helps…

Disc herniation and pain behind the thigh
IN BRIEF A disc protrusion is a bulging of a spinal disc, often without symptoms. A pain behind the thigh can be muscular or, if it originates from the back and is accompanied by tingling or numbness, related to nerve…

Disc herniation and pain in the buttock
IN SHORT A disc protrusion is a disc that bulges without its outer layer being ruptured. If it irritates a nerve root, it can contribute to buttock pain, sometimes accompanied by radiation down the leg, tingling, or numbness. It can…

L5-S1 protrusion and sciatic pain: pathway to the foot
IN BRIEF A L5-S1 disc protrusion is a disc that slightly bulges between the lumbar and sacral vertebrae. If it irritates a nerve root, pain may radiate from the lower back or buttock down the back of the leg to…

L4-L5 protrusion and sciatic pain: possible signs
IN BRIEF A L4-L5 disc protrusion is a bulging of the disc between two lumbar vertebrae. If it irritates the L5 nerve root, it can cause sciatica radiating from the buttock to the side of the leg and the top…
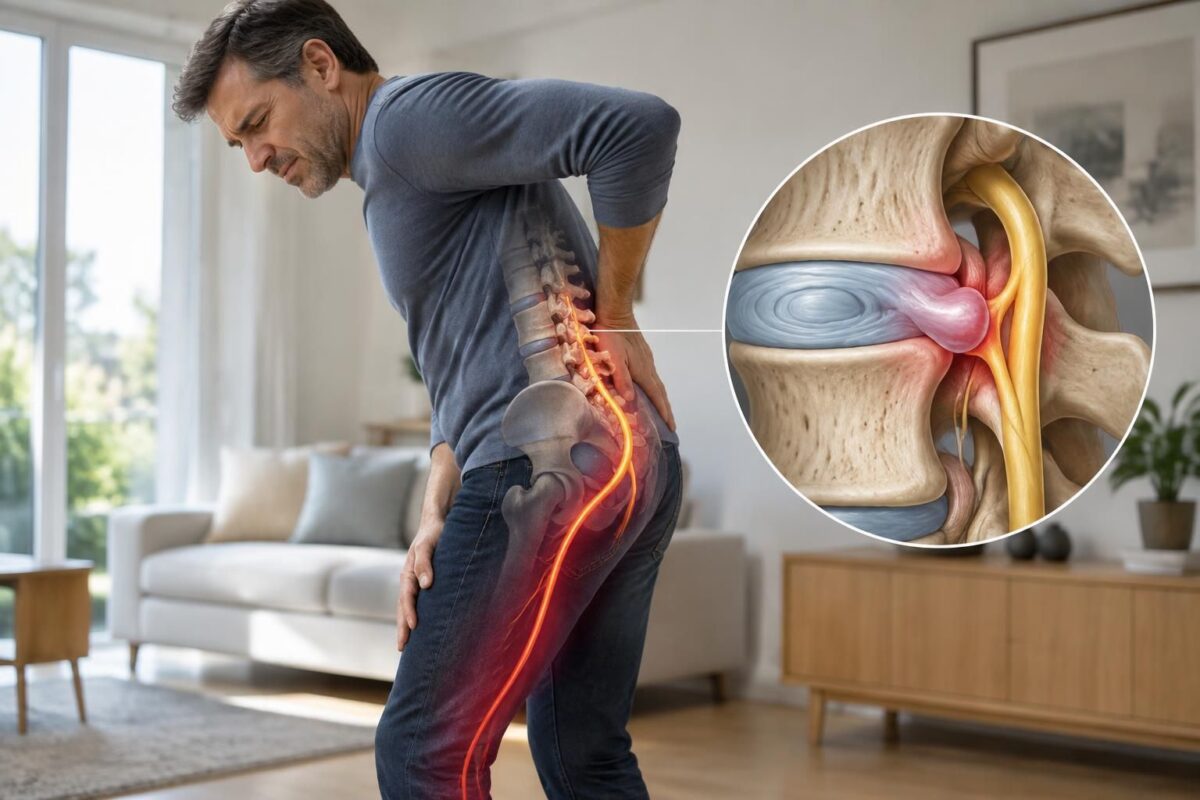
Disc protrusion and sciatica: when the disc touches a nerve root
IN BRIEF A disc protrusion is a disc that extends beyond its usual contour. If it irritates a nerve root, it can contribute to sciatica, with pain radiating into the buttock or leg, sometimes accompanied by tingling or weakness. An…

Dr Sylvain Desforges, B.Sc., D.O., N.D., osteopath, is the founding president of TAGMED and of the ACMA association. He dedicates his practice to chronic spinal pain, low back pain and symptoms compatible with sciatica, particularly when pain radiates toward the buttock, leg, calf, foot or toes.
Through SOS Sciatique, he publishes educational content on sciatica symptoms, possible causes such as disc herniation, disc narrowing, foraminal stenosis or irritation of a lumbar nerve root, as well as non-surgical approaches that may be considered according to the evaluation. At Clinique TAGMED, care may include, depending on the case, motorized neurovertebral decompression, specific osteopathic care or precision percussion.
For an evaluation related to sciatica treatment in Montreal / Mount Royal or sciatica treatment in Terrebonne, please consult the services available at Clinique TAGMED.
Medical disclaimer
The information published on SOS Sciatique is provided for educational purposes only and does not replace a consultation, diagnosis, opinion or treatment provided by a physician or another authorized healthcare professional. The author of this article is neither a medical doctor nor a specialist in a medical specialty recognized by the Collège des médecins du Québec. The osteopathic, manual medicine or functional support approaches described on this site do not constitute medical acts and are not intended to replace medical follow-up.
Consult a physician or emergency service in cases of loss of bladder or bowel control, anesthesia in the saddle area, significant or progressive weakness in the leg or foot, fever, recent trauma, severe pain or rapid worsening of symptoms. For more details, please read our Legal Notice.