Sciatica and pain that worsens in the car
01/08/2026
Sciatica and working at the kitchen table: why the pain may increase
01/08/2026
IN BRIEF
| In brief, sciatica is the irritation or compression of a lumbosacral nerve root that follows the path of the sciatic nerve: pain starting from the lower back or one buttock and radiating into the thigh and leg. This lumbosacral radiculopathy is most often related to a herniated disc or stenosis involving the L4-L5 or L5-S1 roots, and may be accompanied by paresthesias or weakness. Understanding this origin allows for effective and conservative management (activity, rehabilitation) while avoiding unnecessary treatments; the diagnosis relies on clinical examination and, if necessary, targeted imaging. Options range from exercises and manual therapy to more invasive interventions depending on neurological deficits, and surgery is considered in cases of severe signs or cauda equina syndrome. In Montreal, this service is particularly relevant for people suffering from low back pain radiating below the knee and seeking an active and progressive approach. |
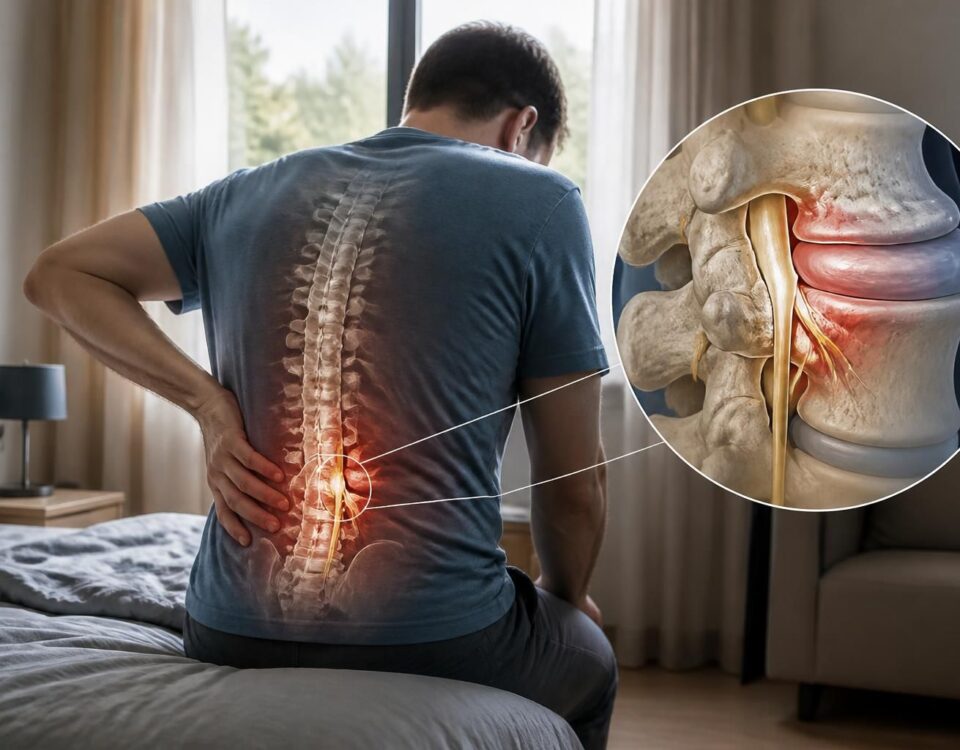
Sciatica is a pain that follows the path of the sciatic nerve. It most often results from irritation or compression of a lumbosacral nerve root (generally the L4-L5 or L5-S1 roots) rather than direct damage to the nerve. This irritation triggers pain that starts from the lower back or buttock and descends into the thigh and leg, sometimes with burning sensations, electricity-like feelings, numbness, and occasionally, muscle weakness. Common causes include a herniated disc and/or lumbar canal stenosis, among other pressures on the spine. The diagnosis is primarily clinical and guides the choice of treatments, which generally favor rehabilitation and conservative measures before any more specialized intervention.
Sciatica is a pain that follows the path of the longest nerve in the body. When a nerve root in the lumbar region is irritated, the pain can spread from the lumbar region to the buttock, then along the thigh and leg, down to the foot. This article explains what it means to have an irritated nerve root, how it comes into play, and what management options exist, with a clinical perspective centered on specialized care such as that offered at the TAGMED Clinic.
What is an irritated nerve root?
Radicular irritation refers to inflammation or compression of a nerve root at the level of the lumbar vertebrae. The pain follows the dermatomal path of the affected root and may be accompanied by paresthesias, numbness, and sometimes, motor deficits. The term lumbosacral radiculopathy is more commonly used when the root is involved in the painful process.
How does it manifest?
Pain often starts in the lower back or buttock and radiates to the back or outside of the thigh and leg. The pain can be sharp, burning, or felt like an electric shock. Sensory signs include tingling and prickling; motor deficits may manifest as muscle weakness in certain muscles of the foot or leg. Symptoms such as coughing or sneezing may amplify the pain, reflecting the radicular nature of the pain.
Common causes and risk factors
- Lumbar herniated disc, particularly at L4-L5 or L5-S1, which compresses a nerve root.
- Foraminal stenosis or spinal stenosis due to degeneration and narrowing of the spinal canal space.
- Spondylolisthesis (sliding of a vertebra) that may narrow the foramina through which nerves exit.
- Piriformis syndrome or extra-spinal lesions that irritate the sciatic nerve outside of the spine.
Risk factors include active adulthood (around 30 to 50 years), smoking, excess weight, and repeated stress on the back. Work style and physical activity also play an important role, as do psychosocial factors that can influence recovery.
Diagnosis and imaging
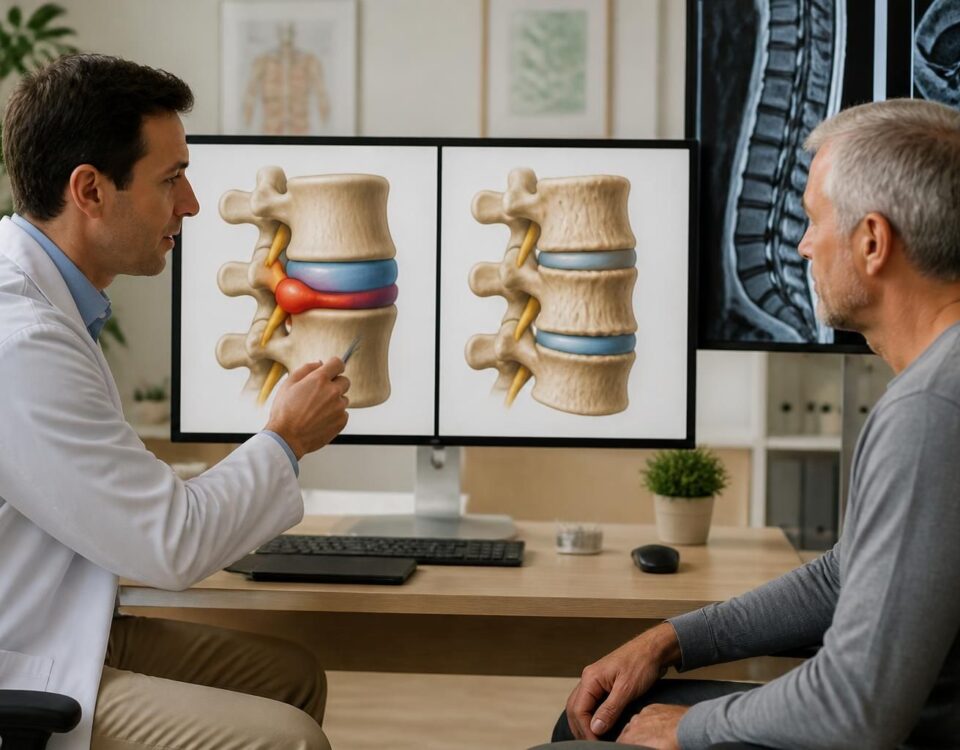
The diagnosis primarily relies on medical history and physical examination. A neurological examination assesses strength, reflexes, and sensitivity, as well as the presence of signs of radicular tension. Magnetic resonance imaging (MRI) or lumbar scanning is not routine but becomes useful when results may change the treatment plan, especially in cases of suspected large herniated discs, tumors, infections, or cauda equina syndrome. It is important not to interpret imaging alone, as protrusions or degenerations can be present without clinically significant pain.
What does the differential diagnosis depend on?
Radicular pain may resemble other conditions like piriformis syndrome, sacroiliac joint arthropathy, or certain non-vertebral pathologies. The diagnosis relies on the correlation between symptoms, the painful area, and examination signs.
Treatment options and management
General approach and clinical framework
Most cases (80%) progress favorably with conservative management over a few weeks. Modern guidance favors maintaining appropriate activity and clear education about the nature of the pain. An individualized approach is preferred, with regular follow-ups and reassessment of needs at each stage.
Specific approaches to consider at the TAGMED clinic
Non-surgical options may be offered, including osteopathic techniques and manual methods tailored to spinal dynamics, as well as functional support measures. In some cases, targeted interventions may be discussed when the expected benefit justifies it and the indications are clear.
Injections and interventional procedures
Epidural injections or blocks may be considered to reduce pain in the short term and facilitate rehabilitation, after individual evaluation and in cases of conservative treatment failure. The decision depends on the clinical context and assessment results.
Surgery and indications
Surgery is considered when there is a progressive neurological deficit, a cauda equina syndrome, or when symptoms persist and significantly limit function after a well-conducted conservative treatment period (usually several weeks to a few months). Surgery can provide quick relief in appropriate cases, but the choice depends on the clinical context and imaging data.
Prevention and Prognosis
Prevention involves weight control, quitting smoking, and maintaining suitable physical activity. Strengthening the abdominal belt and trunk muscles can help, as can avoiding improperly used loads and repeated lumbar bending. The overall prognosis is favorable for most patients, with improvement occurring within a few weeks to a few months. In some persistent cases, an early multidisciplinary approach can improve functional outcomes and reduce the risk of recurrence.
Information for Patients
To learn more about the signs and signals to watch for, you can consult specialized resources on the causes and manifestations of sciatica and on the distinctions between cause and aggravating factor (see the dedicated guides on partner sites).
Useful links and associated resources:
sciatica and signals sent by the leg,
pain in the foot and irritated nerve root,
difference between cause and aggravating factor,
MSD Manuals – Sciatica,
and for general information: The Science of Sciatica. For case-specific information and options at TAGMED clinic, visit TAGMED Clinic.
To enrich your general understanding, you can also consult resources on the causes and treatments offered by specialized teams, including neuro-vertebral approaches and non-surgical options evaluated in your area.
Warning Signs and When to Contact Emergency Services
Report immediately any rapid loss of strength, urinary issues, or a sensation of perineal numbness, progressive weakness of the legs, febrile pain, or unbearable night pain. These signs may indicate a serious syndrome requiring urgent evaluation.
Medical disclaimer: The information and advice provided on this site do not substitute the opinion, diagnosis, or treatment of a health professional. Please note that Dr. Sylvain Desforges, osteopath, is neither a doctor of medicine nor a physician, and is not specialized in a medical specialty as defined by the Collège des médecins du Québec. Manual medicine, functional medicine, and sports medicine as described on this site exclude any treatment or medical diagnosis made by a physician or specialist. Always consult your doctor for any medical questions. For more details, please read our full Legal Notice.
- Origin: Lumbosacral nerve root irritated by a herniated disk or a narrow lumbar canal.
- Mechanism: pressure and inflammation around the root, lowering the pain threshold.
- Pain: radiating along the nerve pathway, from the buttock to the foot.
- Quality: aching, burning, or electric pain, often with paresthesias.
- Neurological signs: possible weakness or loss of sensitivity in the radicular territory.
- Clinical evaluation: history and examination to locate the root (L5 vs S1) and check for deficits.
- Impact on life: may limit walking, sitting position, and sleep.
- Emergencies: signs of cauda equina syndrome, rapid weakness, urinary issues, or perineal anesthesia.
- Initial management: stay active, progressive exercise program, and education.
- When to consult: persistent pain or neurological deficit requiring rapid evaluation.

Sciatica is pain that follows the path of the sciatic nerve. When the lumbar nerve root is irritated or compressed, it triggers pain that can radiate to the buttock, thigh, and leg. This article provides clear recommendations to understand this phenomenon, identify warning signs, and adopt a practical, progressive approach to improving pain and function, without rushing medical decisions.
Understanding What an Irritated Nerve Root Means
A lumbosacral radiculopathy occurs when the nerve root exiting the spine is irritated or compressed. The pain follows a specific path corresponding to the affected root (L5 or S1 being the most common). This irritation can manifest as aching, burning, or electric pain, accompanied by tingling and numbness. The key signal is that the pain is not limited to the back: it extends along the nerve pathway to the leg and may increase with exertion, coughing, or sneezing.

Herniated disc and lumbar osteoarthritis: combined causes of sciatica
IN BRIEF The subject is the association between herniated disc and lumbar osteoarthritis as combined causes of sciatica and femoral neuralgia. This interaction explains the low back pain and nerve irradiations. Benefits and applications: allows differentiation of pain related to…
Herniated disc and foraminal stenosis: possible association
IN BRIEF In brief, a herniated disc and foraminal stenosis are two spinal disorders that can occur together. A herniated disc presents as a protrusion of the intervertebral disc and can compress nerves, while foraminal stenosis refers to the narrowing…
Common Causes and Mechanisms
Herniated Disk and Radicular Compression
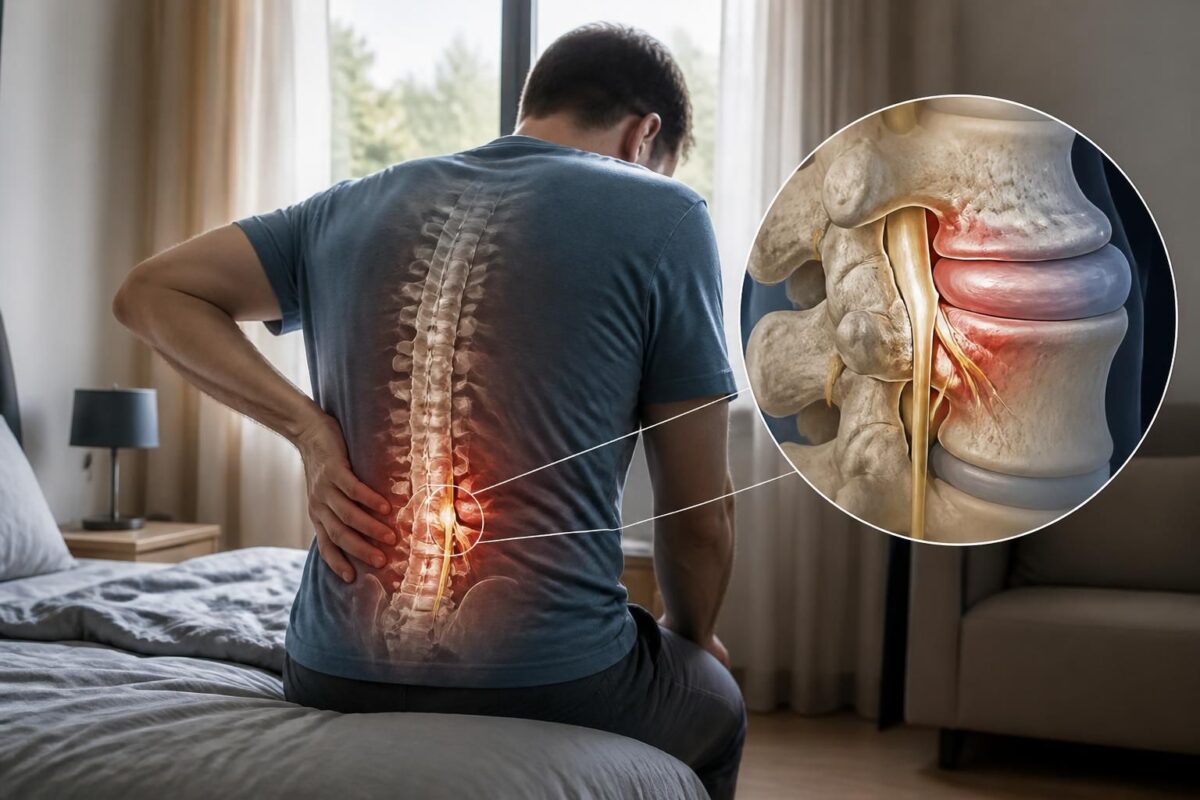
The most common cause is a herniated disk that displaces disc material and compresses the adjacent nerve root. This protrusion is often localized at L4-L5 or L5-S1 and triggers characteristic radicular pain, sometimes associated with weakness or altered sensitivity.
Other Mechanisms and Risk Factors
The foraminal stenosis (narrowing of the nerve passages) and spondylolisthesis can also irritate the roots. Factors such as age, smoking, obesity, and repeated lumbar overload increase the risk. Non-vertebral causes also exist (referred pain or peripheral neuropathy), but it is the radicular mechanisms that most often explain the radiating pain.
Herniated disc and disc pinching: two different mechanisms
IN BRIEF In brief, the disc pinch and herniated disc refer to two distinct mechanisms affecting the intervertebral disc. The disc pinch corresponds to a loss of height of the disc, leading to contact between the vertebral end plates and…

Herniated disc and disc protrusion: terms often混合
IN BRIEF In brief, disc protrusion and herniated disc describe different degrees of the same problem of the intervertebral disc. Protrusion is a contained bulge; herniation is a rupture of the ring with extrusion of the nucleus. Pain primarily depends…
Signs and symptoms to watch for
Beyond pain, one often observes paresthesias (tingling), hypoesthesia in the territory of the affected root and, depending on severity, muscle weakness (for example, difficulty lifting the foot or standing on tiptoes). Pain may worsen when coughing, straining, or sitting too long. Alert signs require prompt evaluation: loss of bladder or bowel control, perineal anesthesia, increasing leg weakness, fever, or major nocturnal pain, which may suggest cauda equina syndrome or another emergency.
Herniated disc and disc bulge: do not confuse
IN BRIEF In brief, the Herniated disc and the disc bulge are two conditions of the spine that differ in their mechanism and prognosis. The disc bulge is a protrusion of the disc without rupture of the fibrous ring, often…
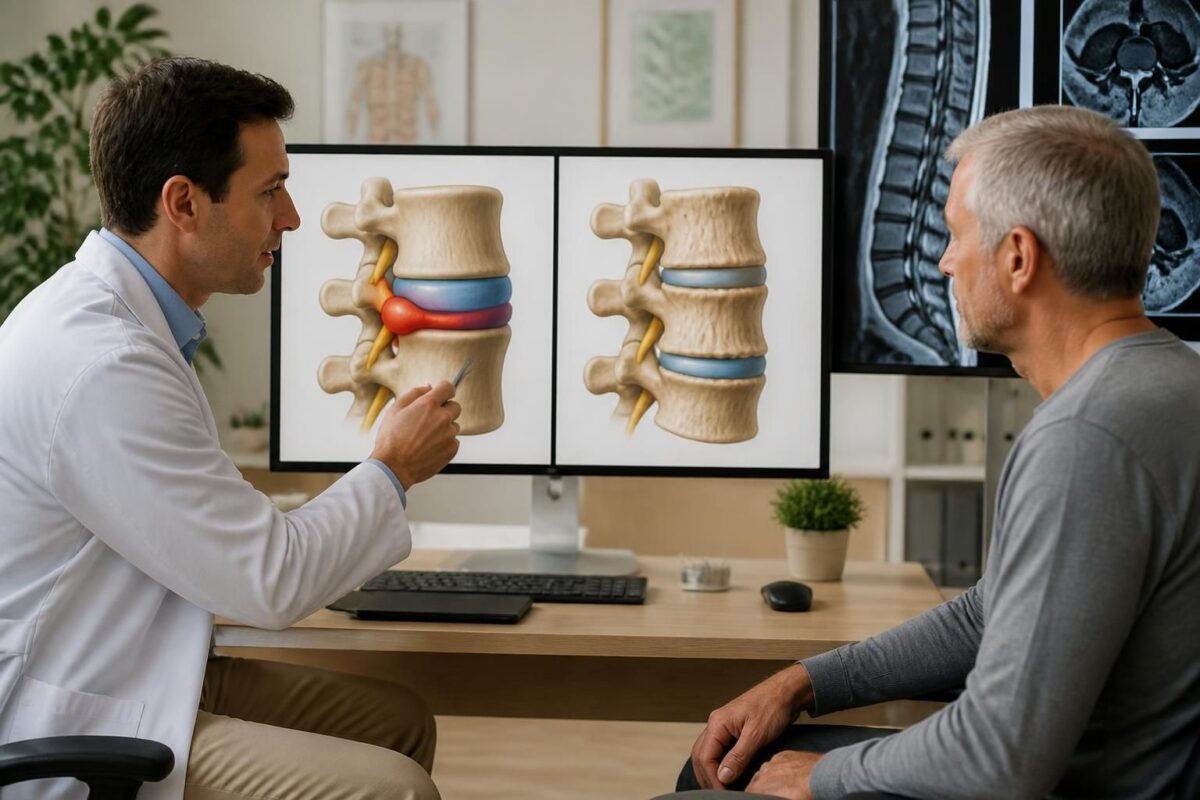
Herniated disc and disc disease: understanding the differences
IN BRIEF In brief, a herniated disc and discopathy are two distinct causes of spinal pain: wear of the intervertebral disc (discopathy) and the protrusion of the gelatinous nucleus that can compress a nerve (herniated disc). Understanding these differences helps…
Practical approach and daily recommendations
Adopt a progressive approach focused on maintaining activity and targeted strengthening. Core stability, flexibility, and posture exercises can improve spinal support and reduce pressure on the irritated root. Favor suitable activities, avoid prolonged bed rest, and prioritize daily actions that protect the back.

Herniated disc and annular tear: possible pain
IN BRIEF In short, Herniated disc and annular tear refer to issues with the intervertebral disc that can cause lower back pain and, at times, pain radiating down the leg. Symptoms vary and can mimic sciatic pain. Treatment favors conservative…
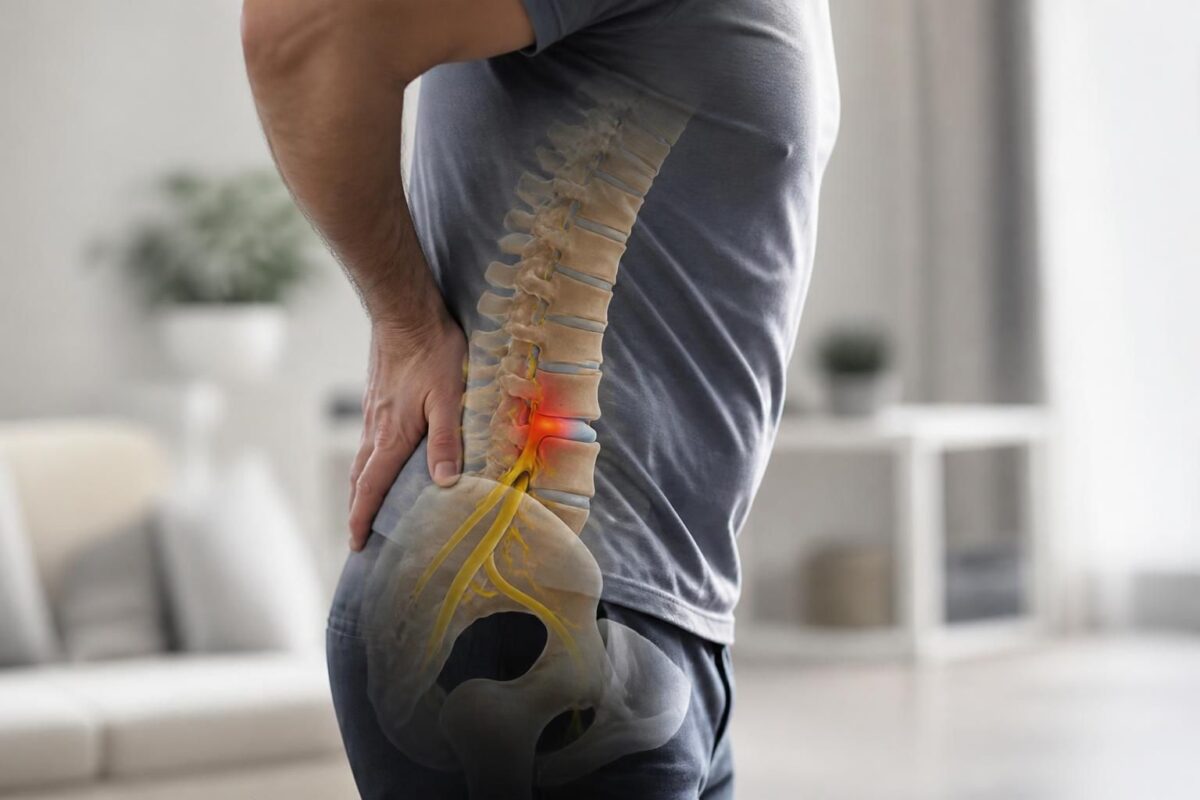
Herniated disc and chemical irritation of the nerve root
IN BRIEF In brief, Herniated disc and chemical irritation of the nerve root describe pain and dysfunction due to compression and inflammatory chemical exchanges affecting a spinal nerve root. This association explains radiating pain, abnormal sensations, and sometimes muscle weakness…
What to do practically right now
1) Stay active with tolerable activities and avoid positions that worsen the pain. 2) Follow a personalized program of strengthening and stretching exercises tailored to your pain and capacity. 3) Work on lifting techniques and load management at work or home. 4) In case of persistent pain, consult for a clinical assessment to evaluate the need for imaging or to explore complementary approaches, such as manual therapies or non-surgical options. 5) In the presence of alert signs, seek immediate attention from emergency services or your primary care doctor.
When to consult and what to expect
Consult promptly if alert signs appear (incontinence, loss of perineal sensation, rapid weakness, fever). In typical cases, improvement is often observed within a few weeks with a conservative approach and appropriate rehabilitation. A specialized evaluation may be considered if symptoms persist despite initial measures or if the clinical context suggests a structural cause requiring specific management.
| Aspect | Concise interpretation |
|---|---|
| Definition | Lumbosacral nerve root irritated by mechanical or inflammatory mechanisms, causing radicular pain along the sciatic nerve. |
| Frequent location | Typical levels L4-L5 or L5-S1; sometimes beyond. |
| Mechanism | Mechanical compression + peri-spinal inflammation lowering the pain threshold. |
| Main symptoms | Pain radiating from the lower back or buttock to the thigh and calf, sometimes burning or electric shock-like; paresthesias. |
| Motor signs | Deficit according to the root: L5 weak dorsiflexion; S1 weak plantarflexion; progression = emergency. |
| Sensory signs | Hypoesthesia in the radicular territory; locally decreased sensitivity. |
| Alert signs | Cauda equina syndrome: urinary issues, saddle anesthesia, bilateral weakness; emergency. |
| Useful diagnosis | Clinical examination; MRI or EMG if discordance or planning for intervention. |
| Initial management | Suitable activity, analgesics, and NSAIDs; physical therapy; injections or surgery if persistent deficit or emergency. |
Testimonials: what it means to have an irritated nerve root in sciatic pain
Testimonial 1: I thought it was just simple lower back pain, until the pain followed the nerve path. I was explained that it wasn’t the nerve itself that was suffering, but its nerve root at the lumbar level that is irritated. This irritated nerve root sends painful signals along the sciatic nerve path, all the way to the buttock and leg. The pain can be throbbing, burning, or like an electric shock, accompanied by tingling or weakness that progresses over time.
Testimonial 2: The pain is often described as an electric shock that starts from the lower back and radiates down the leg, with paresthesias in the back of the thigh and on the shoe. The L5 or S1 root may be involved, and the diagnosis relies as much on the pain path as on the presence of signs such as pain that intensifies with cough or effort. Understanding that irritation of a root can be the real driver of pain changed my way of managing my daily activities.
Testimonial 3: By working with an osteopath, I learned that sciatica is not a single pathology but a set of mechanisms surrounding the nerve root. The goal is not just to calm the pain but to understand where the irritation comes from and how movements, positions, and exercises can free the root and improve function.
Testimonial 4: I realized that some alert signs should not be ignored. Rapidly radiating pain accompanied by weakness or urinary issues may indicate a need for medical emergency. Understanding these signs is learning to protect the nerve root and to act quickly to avoid complications.
Testimonial 5: For me, resuming suitable physical activity and understanding the role of the irritated root has been key. Staying active, learning movement techniques, and strengthening the core has reduced episodes and decreased the fear of movement. Sciatica can be effectively managed when one knows where the irritation is and how to act on it.
As Dr Sylvain Desforges, osteopath and specialist in manual approaches, I place the understanding of nerve roots at the heart of my practice. My background combines osteopathy, naturopathy, and manual medicine, with a concrete implementation of current technologies to support lumbar and radicular pain. At the helm of TAGMED and the ACMA association, I employ an evidence-based approach to help my patients regain their health and well-being, prioritizing information, autonomy, and active rehabilitation when sciatica is suspected of radicular origin.
The “sciatica” is not an isolated disease but a set of clinical signs resulting from irritation or compression of a lumbosacral nerve root. The most common phenomenon is radiculopathy related to a disc herniation or other stenoses that reduce the space around the root at the lumbar level. Irritation may come from a displacement of disc material (protrusion or extrusion) that pinches the root, or from a chronic narrowing of the spinal canal. These mechanisms trigger pain that follows the dermatomal path of the affected root, most often L5 or S1, and may be accompanied by paresthesias, numbness, and sometimes muscular weakness.
Beyond the label “sciatica,” it is useful to distinguish the different possible origins that share the same painful territory: disc herniation with radiculopathy, lumbar stenosis, spondylolisthesis, or a piriformis syndrome that can mimic radiculopathy without vertebral disorder. This distinction is essential because it influences the choice of treatments and the pace of rehabilitation. An irritated root does not resolve solely through pain: it reflects a mechanical and inflammatory mechanism that requires an adapted and gradual approach.
Clinically, the pain follows the path of the root and can be described as dull, burning, or electric. Numbness and tingling often accompany the pain, and muscular weakness may appear when compression persists. Coughing, sneezing, or straining can exacerbate symptoms, demonstrating the link between intra-abdominal pressure and stress on the nerve root. Warning signs, such as progressive weakness, altered sphincter control, or pain associated with urinary symptoms, require urgent medical evaluation.
In my approach, the diagnosis is based on the medical history and neuro-functional examination: precise location of the pain, radicular provocation tests, and evaluation of strength, reflexes, and sensitivity. Imaging, when necessary to guide treatment, is used in a targeted manner and does not replace clinical evaluation. The goal is always to distinguish true radiculopathy from other causes of radiating pain, in order to propose an appropriate and effective care plan.
The treatment first emphasizes conservative and active measures. I focus on patient education, maintaining appropriate physical activity, and a personalized exercise program centered on trunk strengthening, mobility improvement, and a gradual return to daily activities. Manual techniques and complementary modalities can be used in a targeted manner and as a complement to an exercise protocol, with particular attention to the psychological impact and fear of movement. Medical-technical interventions, when necessary, prioritize safe and evidence-based options, without systematically resorting to surgery, except in cases of significant neurological deficit or emergencies.
The prognosis of sciatica is generally favorable: many patients observe improvement within weeks to months with appropriate management and progressive rehabilitation. Prevention involves controlling modifiable risk factors, such as maintaining a healthy weight, quitting smoking when necessary, regular physical activity, and strengthening the deep muscles of the back and trunk. A proactive and individualized approach, combining information, movement, and support, is key to limiting recurrences and optimizing function.
If you wish to discuss your situation or obtain a personalized assessment, do not hesitate to contact the TAGMED Clinic, where a dedicated team can assist you toward a better quality of life and sustainable functional recovery.
This introduction quickly summarizes the topic: an irritated nerve root in the context of sciatica is the result of a process combining a mechanical mechanism and an inflammatory reaction around the lumbar roots. Understanding this phenomenon helps to distinguish pain that radiates along the pathway of the nerve and the signs that indicate appropriate management, ranging from conservative measures to possible intervention when necessary.
An irritated nerve root means that the pain and symptoms primarily originate from the nerve root located at the lumbar level, rather than from simple back pain. The most frequent causes include a disc herniation that compresses or irritates the root, a lumbar stenosis that restricts space around the nerve, or a spondylolisthesis causing vertebral deviation. The most commonly affected site is between L4-L5 and L5-S1, leading to pain that follows the dermatomal pathway of the concerned nerve and may be associated with paresthesias, muscular weakness, and a burning or electric-like sensation.
Clinically, radicular pain spreads from the lower back or buttock down to the leg, and may be accompanied by sensory or motor disturbances depending on the affected root. The exact location depends on the affected level: for example, L5 may affect the outer edge of the foot and toe extension, while S1 may alter the sole of the foot and the gastrocnemius muscle. Pain is often aggravated by movements that increase pressure on the spine, such as coughing, sneezing, or straining, and may be more intense in the leg than in the back.
Warning signs necessitate prompt consultation: cauda equina syndrome (urinary disturbances, perineal anesthesia, weakness in both legs), associated fever, unexplained weight loss, or severe nighttime pain. In these situations, we refer to a neurosurgical emergency, and action must be taken immediately.
The diagnosis is primarily based on the medical history and neurological examination. Magnetic resonance imaging (MRI) is the preferred imaging tool when results influence therapeutic decisions (for example, suspicion of significant disc herniation or surgical planning). CT scans may be useful if MRI is unavailable or contraindicated. An EMG may be considered to specify the level and age of the injury when the clinical picture and clinical exams are discordant.
Regarding treatment, a conservative approach remains the first intention in most cases: maintaining appropriate physical activity, educating the patient, and targeted exercise programs to strengthen the abdominal belt and deep back muscles while improving mobility and stability. Non-steroidal anti-inflammatory drugs and pain relievers may be useful in the short term; epidural injections remain an option when medical treatment does not provide sufficient relief. Surgery is considered when neurological deficits progress, when cauda equina syndrome is suspected, or after a well-conducted conservative treatment fails over an appropriate period, using minimally invasive techniques as needed.
Prevention and rehabilitation play a key role. Active prevention involves maintaining a healthy weight, quitting smoking, engaging in regular physical activity, and strengthening the trunk muscles, as well as ergonomic measures at work and a gradual return to activity after a crisis. The prognosis is generally favorable: many episodes improve within a few weeks to a few months without requiring surgery, but chronicity can occur if psychosocial factors or problematic habits persist.
For further reading, consult the following additional resources: Treatment of sciatica in Terrebonne (symptoms, causes, and care plan), Treatment of sciatica in Montreal – mechanical approach, Sciatica: nerve irritation – Symptoms and treatments, Radiculopathy and nerve root compression, Sciatica pain in Terrebonne – difficult walking, Sciatica and poorly positioned feet – impact on posture, Sciatica – causes, symptoms, and treatments, Pain aggravated by lumbar twists, Sciatic nerve – understand and alleviate.

Dr Sylvain Desforges, B.Sc., D.O., N.D., osteopath, is the founding president of TAGMED and of the ACMA association. He dedicates his practice to chronic spinal pain, low back pain and symptoms compatible with sciatica, particularly when pain radiates toward the buttock, leg, calf, foot or toes.
Through SOS Sciatique, he publishes educational content on sciatica symptoms, possible causes such as disc herniation, disc narrowing, foraminal stenosis or irritation of a lumbar nerve root, as well as non-surgical approaches that may be considered according to the evaluation. At Clinique TAGMED, care may include, depending on the case, motorized neurovertebral decompression, specific osteopathic care or precision percussion.
For an evaluation related to sciatica treatment in Montreal / Mount Royal or sciatica treatment in Terrebonne, please consult the services available at Clinique TAGMED.
Medical disclaimer
The information published on SOS Sciatique is provided for educational purposes only and does not replace a consultation, diagnosis, opinion or treatment provided by a physician or another authorized healthcare professional. The author of this article is neither a medical doctor nor a specialist in a medical specialty recognized by the Collège des médecins du Québec. The osteopathic, manual medicine or functional support approaches described on this site do not constitute medical acts and are not intended to replace medical follow-up.
Consult a physician or emergency service in cases of loss of bladder or bowel control, anesthesia in the saddle area, significant or progressive weakness in the leg or foot, fever, recent trauma, severe pain or rapid worsening of symptoms. For more details, please read our Legal Notice.